



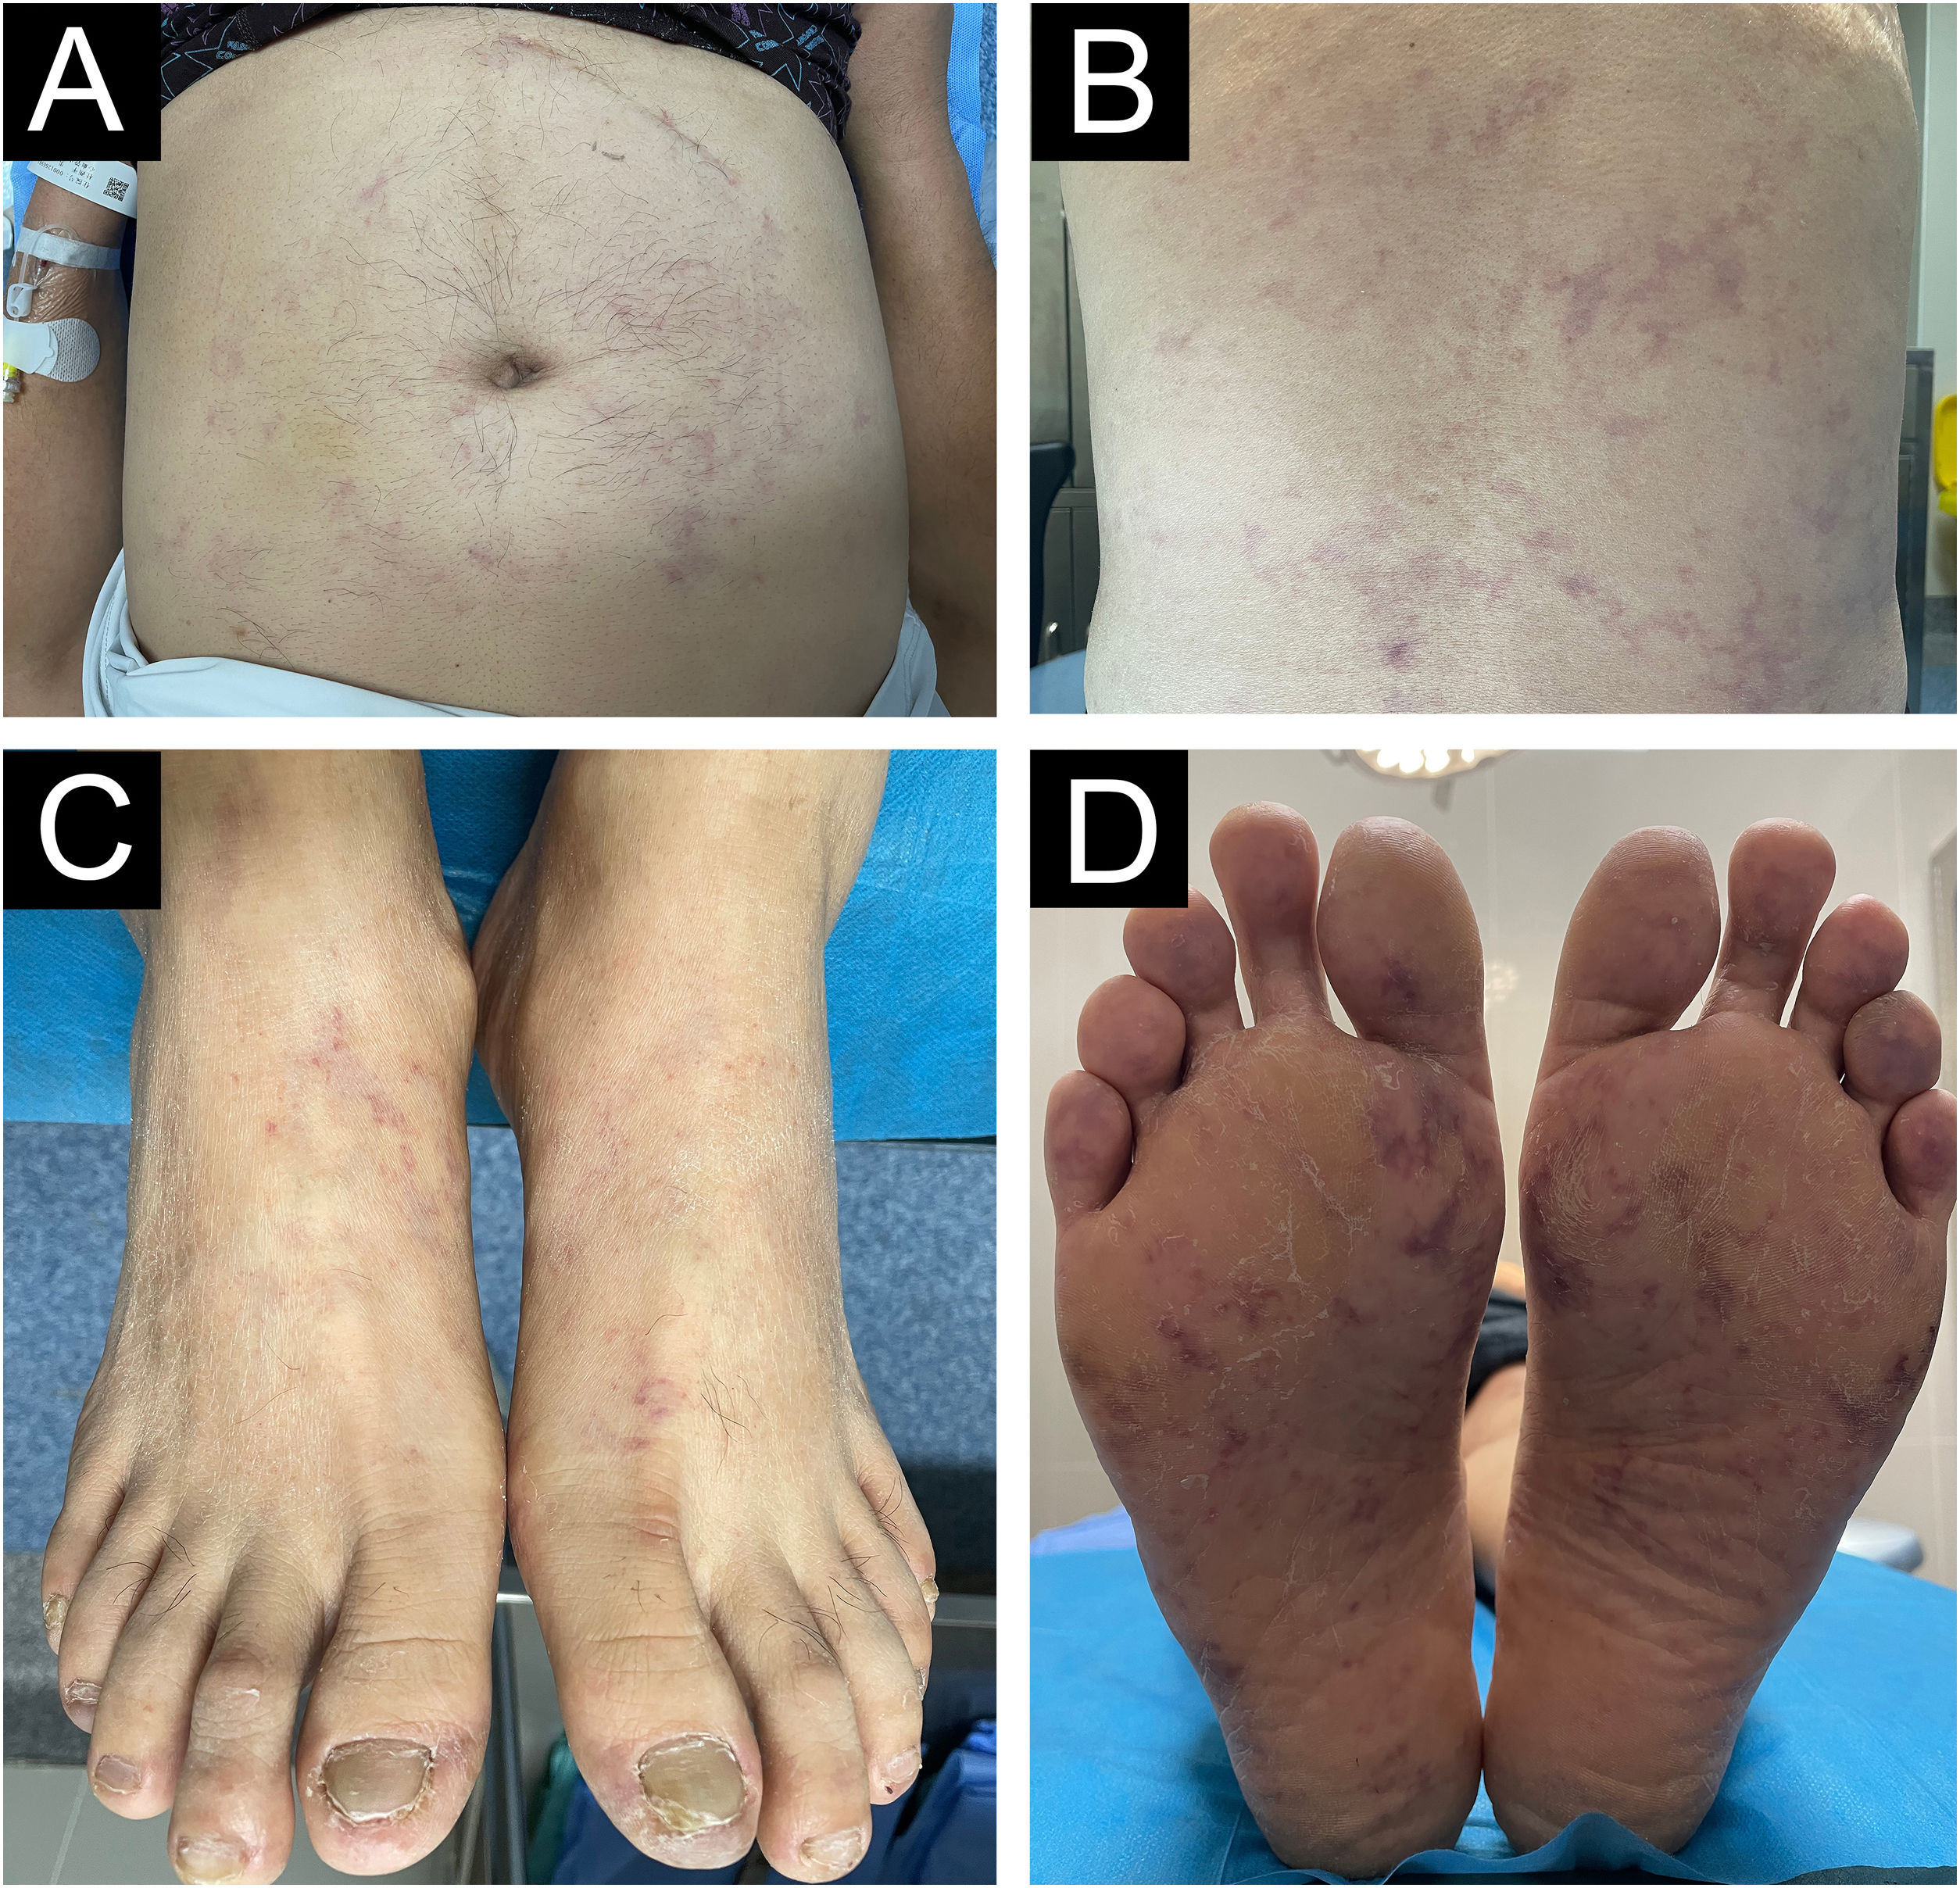
A 56-year-old male with a decade-long medical history marked by type 2 diabetes mellitus, hyperlipidemia, hypertension, and coronary artery disease underwent Percutaneous Coronary Intervention (PCI) one month ago. The patient presented to the emergency department with a three-day history of toe pain. Physical examination revealed the presence of blue reticulated patches on the abdomen, back, thighs, lower extremities, and feet, occasionally accompanied by purpuric plaques. The morphological diagnosis of the skin was livedo reticularis and reticular purpura (Fig. 1). On palpation, the toes were noted to be cold and painful. The dorsalis pedis and posterior tibial pulses were found to be within normal parameters. Laboratory tests revealed elevated levels of eosinophils, triglycerides, serum creatinine, and urea, along with decreased levels of complement, prolonged Activated Partial Thromboplastin Time (APTT), and increased plasma D-dimer. The peak creatinine level was 84.9 μmol/L (reference range: 53–123 μmol/L). The inflammatory markers revealed an erythrocyte sedimentation rate (ESR) of 37 mm/h (reference range: 0–15 mm/h) and C-Reactive Protein (CRP) of 27.53 mg/L (reference range: < 10 mg/L).

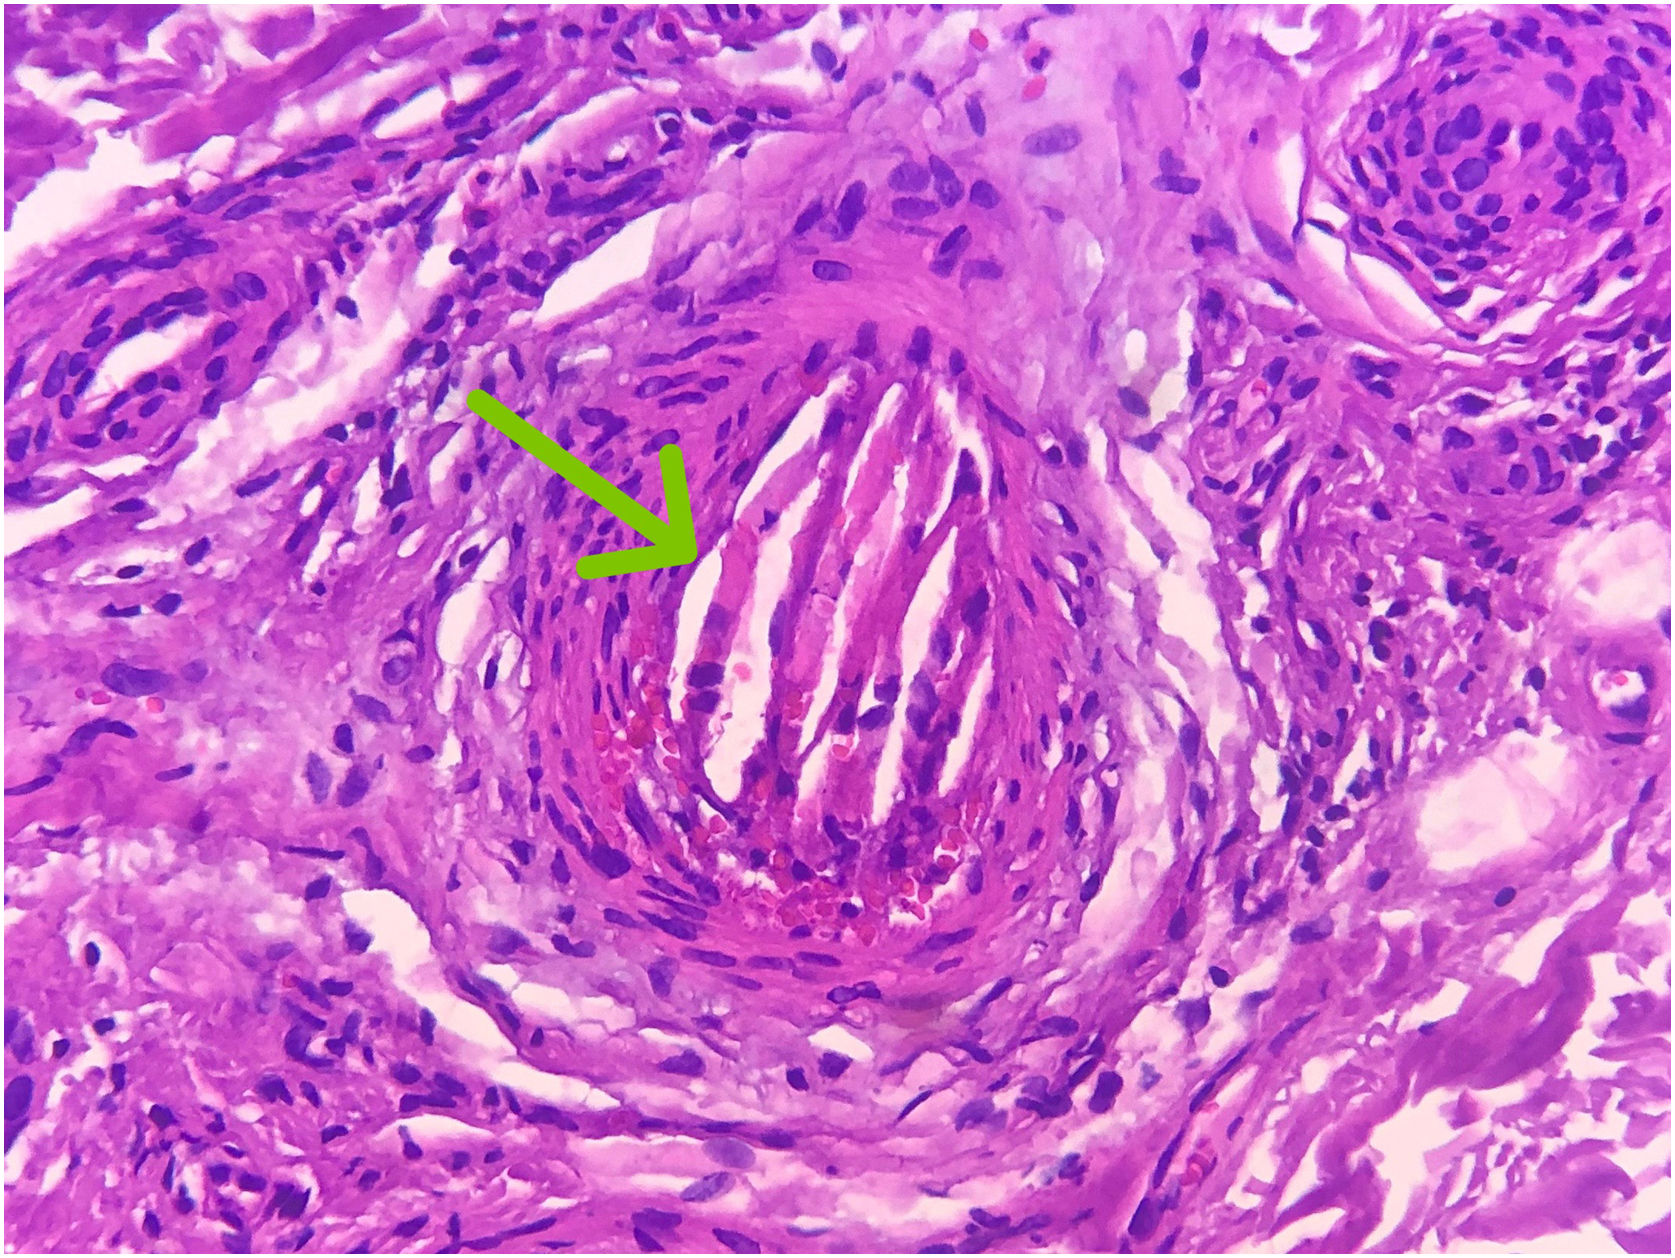
Urinalysis revealed a peak total urinary protein excretion of 477 mg over a 24 hour period, with no other significant abnormalities detected. A subsequent nephrology consultation recommended hormone therapy if deemed necessary, in addition to dynamic monitoring of coagulation function, complete blood count, urinalysis, and urine output changes. Bilateral lower extremity arterial Doppler ultrasound revealed thickened, rough vessel walls with atherosclerotic plaque formation in the bilateral external iliac, femoral, popliteal, anterior tibial, posterior tibial, and dorsalis pedis arteries. Suboptimal blood flow was observed in the bilateral anterior tibial and dorsalis pedis arteries. A skin biopsy revealed the presence of cholesterol clefts within the small vascular lumina (Fig. 2). The patient was diagnosed with Cholesterol Embolism Syndrome (CES) on the basis of the following: the characteristic cutaneous manifestations, the laboratory findings, and the skin biopsy results.

Cholesterol Embolism Syndrome (CES) is defined as the release of cholesterol crystals from atherosclerotic plaques in the arterial wall. These crystals are transported via the arteriolar circulation to downstream terminal organs, resulting in systemic ischemia and inflammatory injury in multiple organs. It has been associated with intravascular interventional procedures, such as angiography and thrombolytic therapy, which have been demonstrated to cause rupture of atherosclerotic plaques in large vessels, resulting in embolization of small vessels.
Laboratory tests typically reveal eosinophilia (increased blood eosinophils), elevated levels of inflammatory markers such as C-Reactive Protein (CRP) and Erythrocyte Sedimentation Rate (ESR), along with decreased complement levels. It has been established that certain organs are particularly susceptible to cholesterol embolism, including the skin, kidneys, brain, gastrointestinal tract, and skeletal muscles.1
According to extant literature, Cholesterol Embolism Syndrome (CES) is a relatively rare but serious complication that can occur following cardiac catheterization. The incidence of CES after coronary intervention has been documented as 1.4%.2
In a significant proportion of cases, skin involvement is observed, manifesting in the form of reticular purpura, gangrene, ulcers, nodules, and purpura. The prevalence of this manifestation can reach up to 96%. Skin biopsy is a diagnostic modality that can provide a definitive diagnosis. The typical hallmark of this condition is the presence of needle-shaped clefts (or acicular clefts) within the lumina of small arteries in the affected skin.
Despite the fact that symptom overlap frequently results in underdiagnosis of the disease, CES should be considered a probable diagnosis in patients presenting with characteristic cutaneous manifestations (e.g., blue toes, livedo reticularis, and petechiae), particularly following vascular interventional procedures.
Research has demonstrated that Cholesterol Embolism Syndrome (CES) is, in fact, an autoinflammatory disease. This is characterized by the induction of inflammasome pathways, such as NLRP3 and IL-1, by Cholesterol Crystals (CC).3 The histological analysis of reticular purpura is of paramount importance in order to distinguish between the underlying causes of the condition, namely vascular occlusion or lesions affecting the vessel wall (including conditions such as infection or vasculitis).
Further differential diagnoses must be considered, including, but not limited to, arterial thromboembolism. The latter typically leads to acute ischemic infarction, whereas CES manifests as a subacute condition, and thus their respective treatments differ considerably. Conversely, anticoagulation, thrombolysis, and interventional procedures employed in the treatment of arterial thromboembolism are not applicable to CES. Vasculitides and vasculopathies (e.g., Reynaud's disease, systemic lupus erythematosus, polyarteritis nodosa, thromboangiitis obliterans, infections, cryoglobulinemia, and Antiphospholipid Syndrome [APLS]) frequently exhibit clinical features analogous to those observed in CES, characterized by reticular hyperplasia. Early identification of these conditions is imperative to prevent further instances of ischemia and to reduce other manifestations of atherosclerosis.
With regard to treatment options, the emphasis on secondary prevention of cardiovascular diseases is of paramount importance for these patients, encompassing the administration of statins, antiplatelet agents, smoking cessation, and strict regulation of blood pressure, weight, and blood glucose levels. Furthermore, anti-inflammatory therapies (e.g., corticosteroids and cyclophosphamide) represent a viable treatment option. The patient was treated with a statin, prednisone, clopidogrel, and antihypertensive agents. Advanced age, diabetes mellitus, and progression to End-Stage Renal Disease (ESRD) have been demonstrated to be associated with an elevated risk of mortality.4 The extant case reports indicate that treatment with corticosteroids, pentoxifylline, or iloprost is beneficial for CES. The rationale for the utilization of corticosteroids in the management of cholesterol embolism syndrome is predicated on the principle of attenuating inflammation at the site of distal arterial emboli. This approach enables the body to initiate the mechanisms necessary for the clearance of microemboli and the prevention of progressive ischemia.5 Despite the present utilization of corticosteroid therapy, the long-term effects of corticosteroid treatment and effective tapering regimens require more rigorous investigation through Randomized Controlled Trials (RCTs).
The course of the condition is variable, with some patients experiencing a self-limiting course, while others progress to renal failure and death. In view of the advanced atherosclerosis of the Carotid Arteries (CAS) and the presence of concomitant cardiovascular diseases, the prognosis is frequently poor.
ORCID IDHaiying Hui: 0000-0003-4587-9453.
Ethical approvalNone.
Ethics statementNone.
Data availability statementNone.
Research data availabilityDoes not apply.
Financial supportNone declared.
Author’s contributionYang Xian: Analysis and interpretation; Effective participation in research orientation; Data collection; Preparation and writing of the manuscript.
Haiying Hui: Intellectual participation in propaedeutic and therapeutic management of studied cases; Manuscript critical review; Study conception and planning.
None declared.
Study conducted at the Department of Dermatology, Shaanxi Provincial People’s Hospital, Xi’an, Shaanxi, China.


