



Basal Cell Carcinoma (BCC) is the most common skin cancer worldwide; however, its clinical and dermoscopic features in darker phototypes remain underexplored. Research predominantly based on lighter skin tones may hinder the recognition of BCC in individuals with skin of color, in whom pigmentation often masks classical diagnostic features such as translucency and telangiectasias.1 In these patients, dermoscopy becomes an essential diagnostic tool, as studies have shown that BCC in skin of color frequently presents as pigmented lesions that may mimic other benign or malignant conditions.2,3 Additionally, the underrepresentation of darker phototypes in BCC-related clinical studies ‒ fewer than half of which report participants’ skin color or phototype ‒ limits the applicability of existing diagnostic frameworks.4
This study aimed to characterize the epidemiological, clinical, dermoscopic and histopathological aspects of BCCs in Brazilian patients with Fitzpatrick skin phototypes IV and V.
A retrospective analysis was performed on 76 histopathologically confirmed BCCs from 63 patients. Images were acquired using Canon PowerShot, Nikon 1, DermLite DL-3/DL4, or Fotofinder dermoscopes. Three dermatologists evaluated the images together and reached a consensus on each lesion’s characteristics.
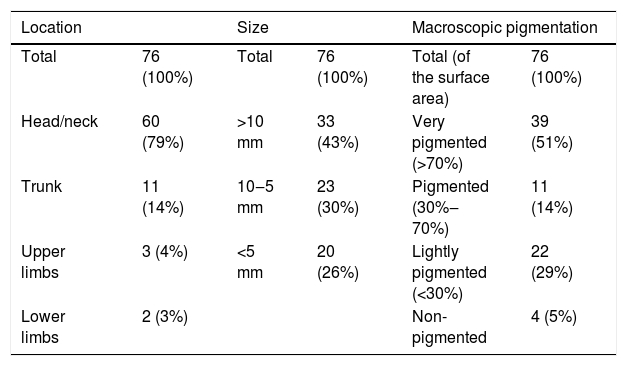
Among the 63 patients, 30 were female and 33 male, with a mean age of 70-years (range 49–84). The clinical characteristics of the tumors are summarized in Table 1.
Clinical aspects of basal cell carcinomas.
| Location | Size | Macroscopic pigmentation | |||
|---|---|---|---|---|---|
| Total | 76 (100%) | Total | 76 (100%) | Total (of the surface area) | 76 (100%) |
| Head/neck | 60 (79%) | >10 mm | 33 (43%) | Very pigmented (>70%) | 39 (51%) |
| Trunk | 11 (14%) | 10‒5 mm | 23 (30%) | Pigmented (30%‒70%) | 11 (14%) |
| Upper limbs | 3 (4%) | <5 mm | 20 (26%) | Lightly pigmented (<30%) | 22 (29%) |
| Lower limbs | 2 (3%) | Non-pigmented | 4 (5%) | ||
Histopathologically, 37 (49%) of the BCCs were classified as nodular, 19 (25%) as superficial, 2 (3%) as infiltrative, and 15 (20%) exhibited mixed histology. The subtype could not be determined in 3 (4%) cases.
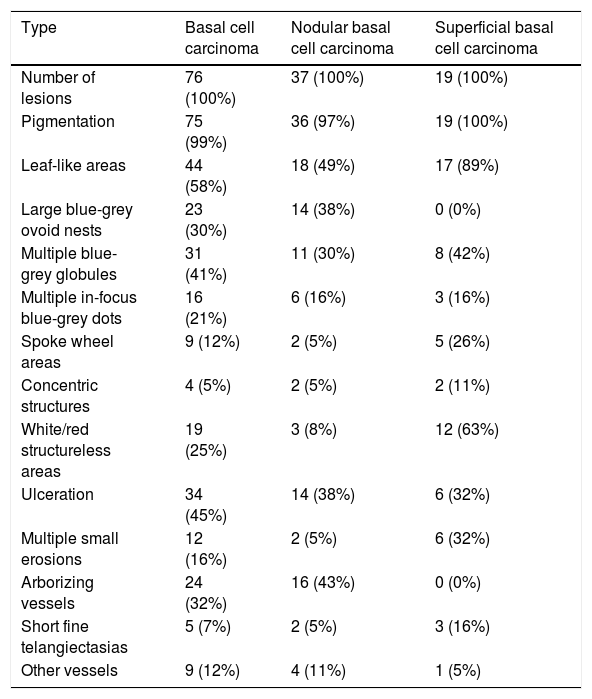
Regarding the proportion of the tumor area that showed pigmentation under dermoscopy, 34 (45%) lesions were highly pigmented (>70% of the surface area), 17 (22%) were moderately pigmented (30%–70% of the surface area), 24 (31%) were lightly pigmented (<30% of the surface area), and only one (1%) showed no pigmentation. Table 2 summarizes the frequency of the other dermoscopic features across all tumors and compares their distribution between nodular and superficial subtypes.
Dermoscopic features of basal cell carcinomas.
| Type | Basal cell carcinoma | Nodular basal cell carcinoma | Superficial basal cell carcinoma |
|---|---|---|---|
| Number of lesions | 76 (100%) | 37 (100%) | 19 (100%) |
| Pigmentation | 75 (99%) | 36 (97%) | 19 (100%) |
| Leaf-like areas | 44 (58%) | 18 (49%) | 17 (89%) |
| Large blue-grey ovoid nests | 23 (30%) | 14 (38%) | 0 (0%) |
| Multiple blue-grey globules | 31 (41%) | 11 (30%) | 8 (42%) |
| Multiple in-focus blue-grey dots | 16 (21%) | 6 (16%) | 3 (16%) |
| Spoke wheel areas | 9 (12%) | 2 (5%) | 5 (26%) |
| Concentric structures | 4 (5%) | 2 (5%) | 2 (11%) |
| White/red structureless areas | 19 (25%) | 3 (8%) | 12 (63%) |
| Ulceration | 34 (45%) | 14 (38%) | 6 (32%) |
| Multiple small erosions | 12 (16%) | 2 (5%) | 6 (32%) |
| Arborizing vessels | 24 (32%) | 16 (43%) | 0 (0%) |
| Short fine telangiectasias | 5 (7%) | 2 (5%) | 3 (16%) |
| Other vessels | 9 (12%) | 4 (11%) | 1 (5%) |
Compared with previous reports, the proportion of pigmented BCCs in this series was markedly higher, consistent with findings from non-Caucasian populations.5,6 Highly pigmented lesions (>70% of the surface pigmented) accounted for 45% of cases, whereas among pigmented BCCs in lighter skin tones, only 7%–13% are highly pigmented.7 This contrast reinforces pigmentation as a key diagnostic feature of BCC in darker phototypes.
Leaf-like areas were the most frequent dermoscopic structure, appearing in 58% of lesions ‒ higher than frequencies described in most prior studies, with a comparable finding only in an Indian population of similar phototype.8,9 This finding suggests that leaf-like areas may serve as an important diagnostic clue for BCC in darker skin. The predominance of pigmentation may obscure classical dermoscopic features such as arborizing vessels and short fine telangiectasias, which were less frequently detected in this study.
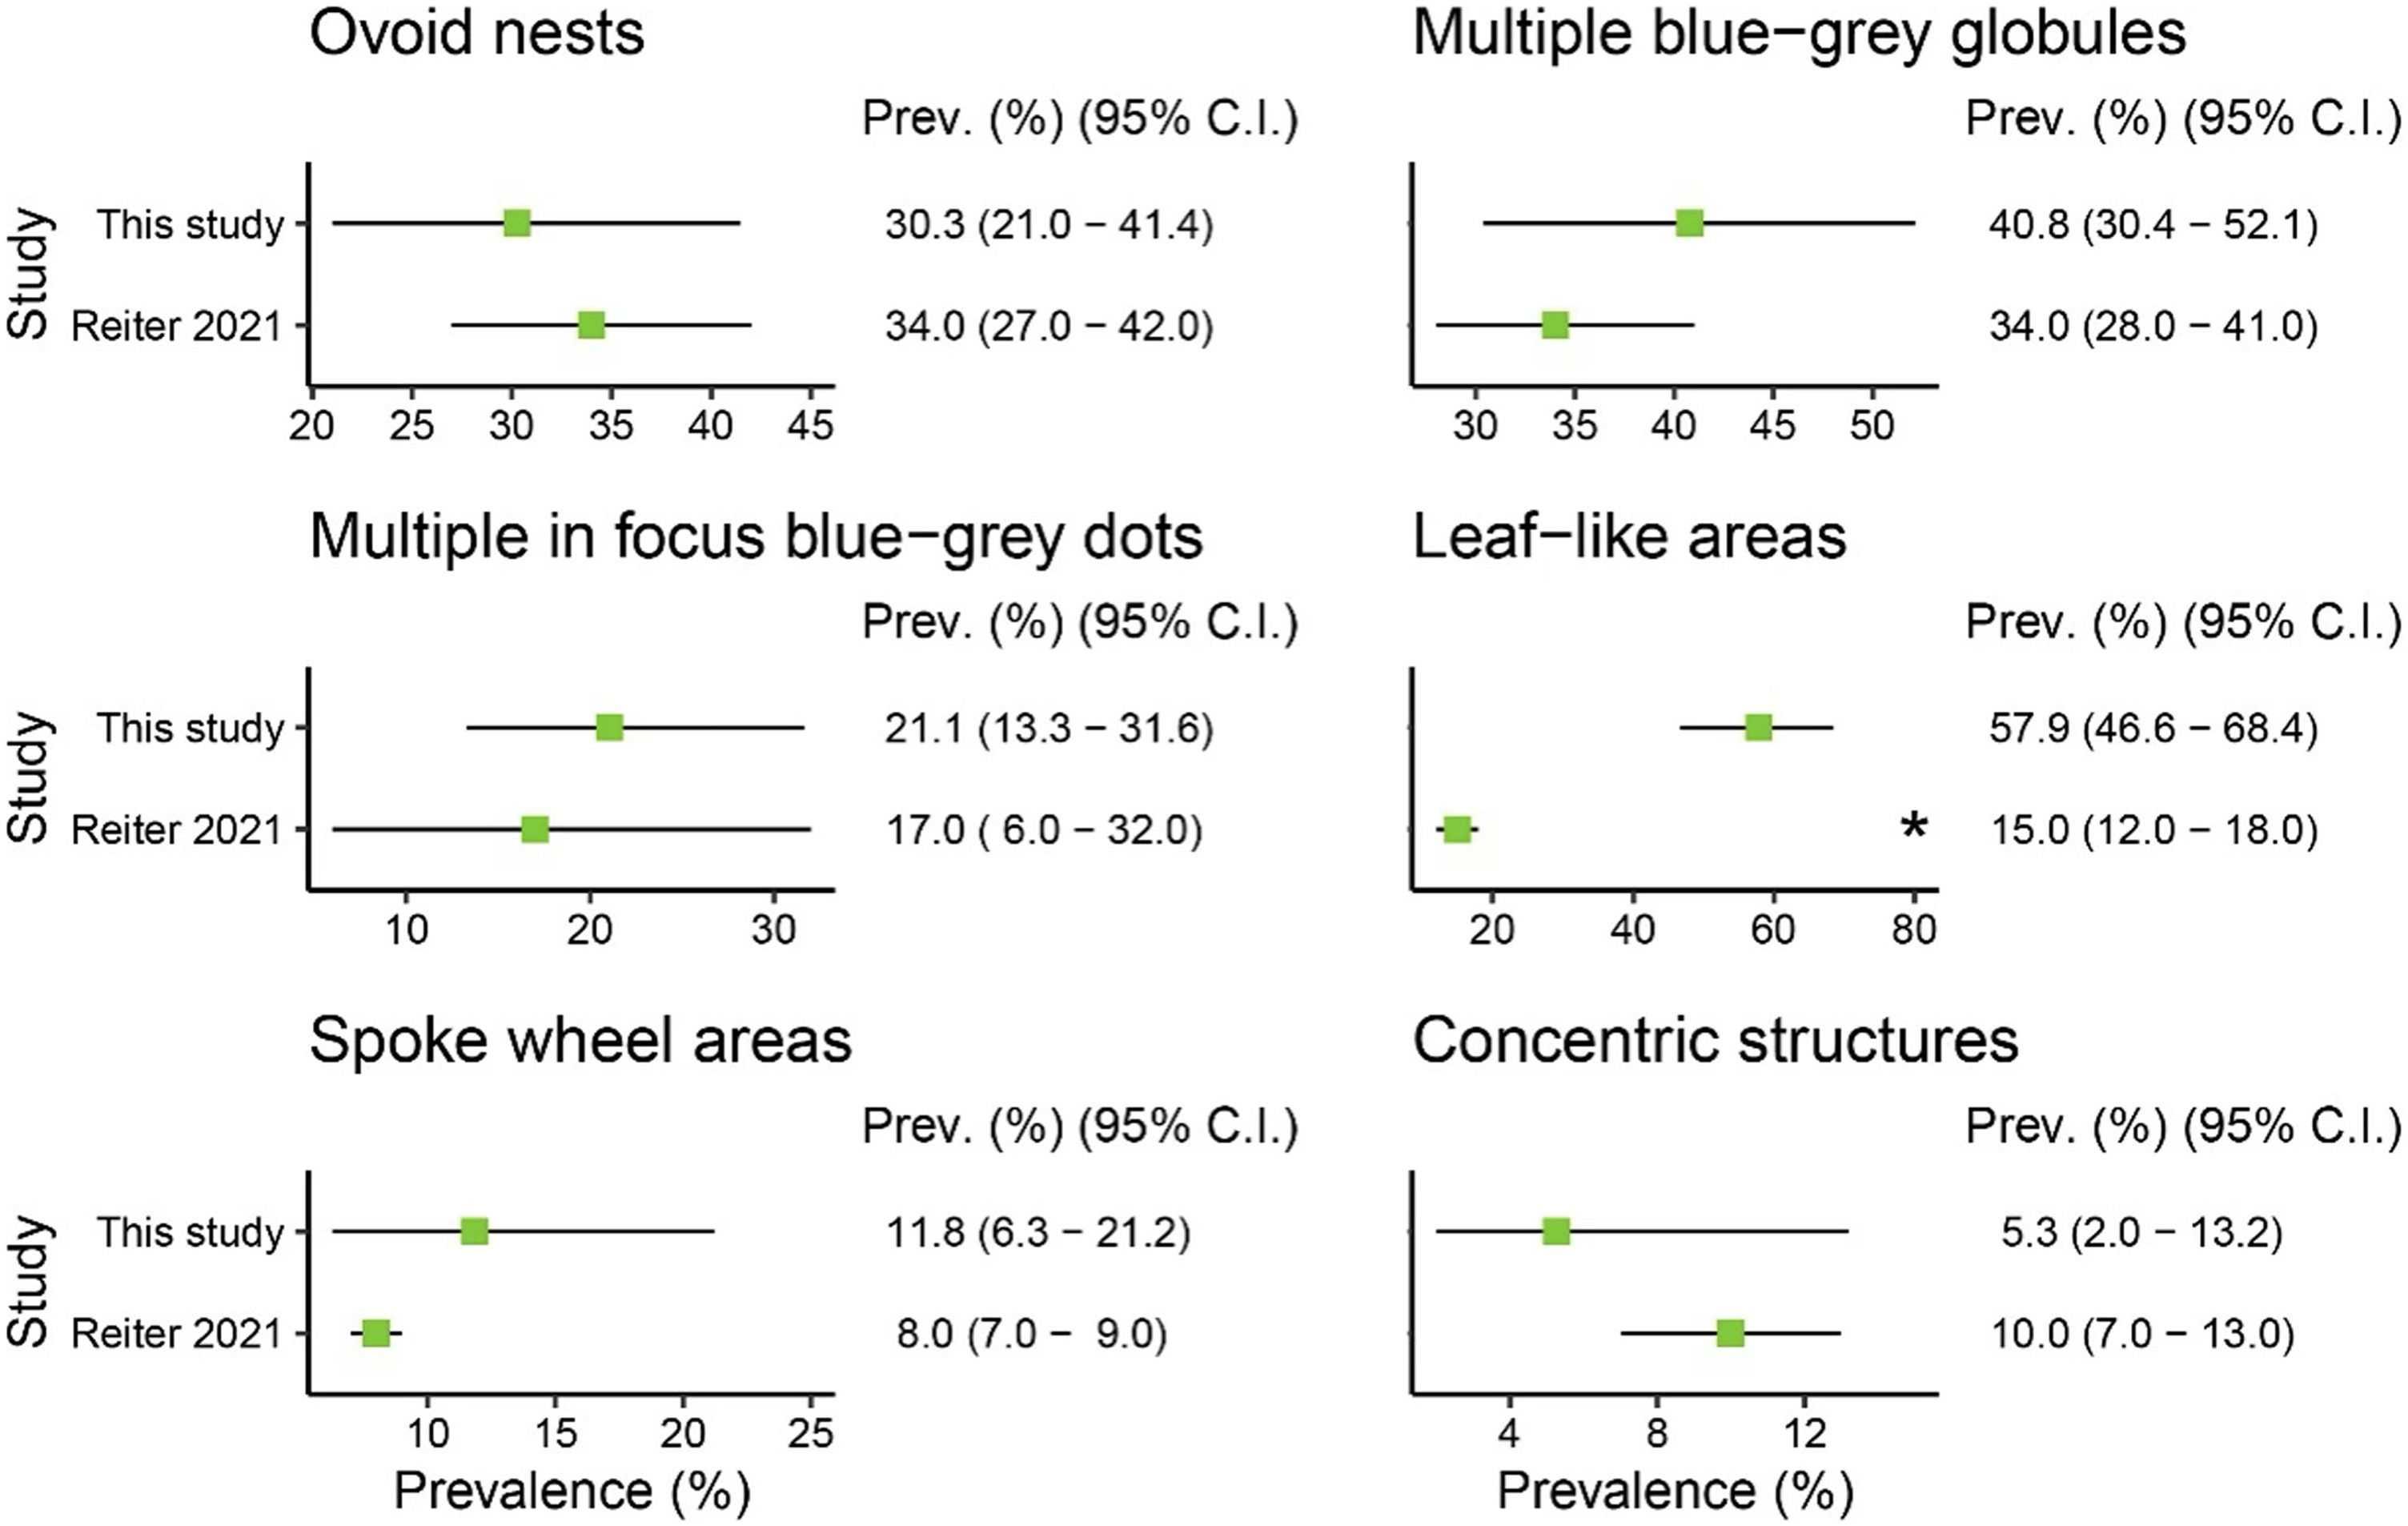
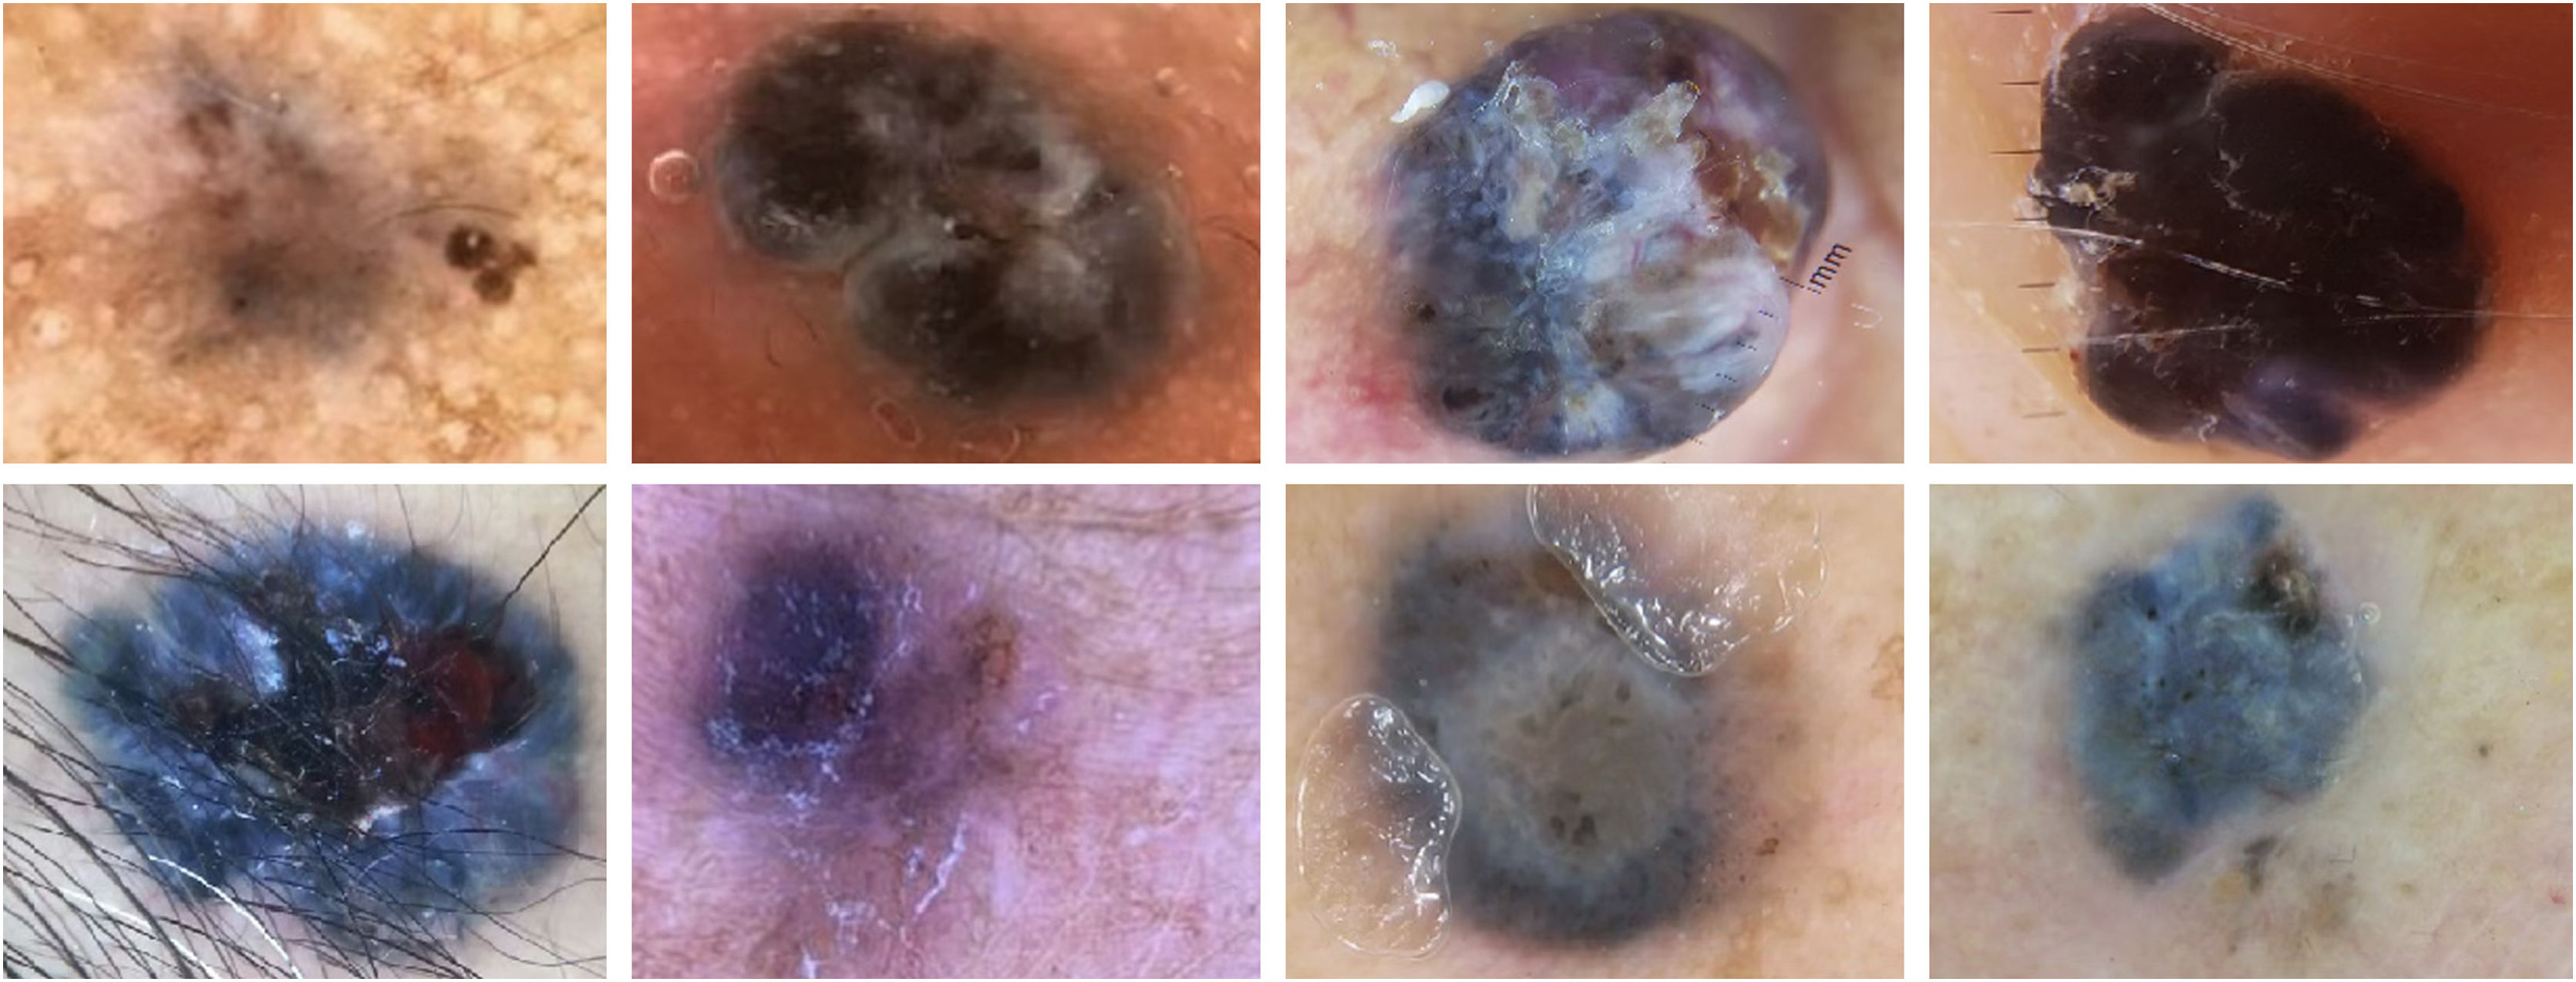
The data on pigmented structures were also compared with a systematic review published in 2021 by Reiter et al., which quantified the prevalence of dermoscopic structures present in BCCs.10 Only the leaf-like areas were significantly more prevalent in our study compared to the systematic review (p < 0.05; Fig. 1). This result may seem unexpected, given the much higher degree of pigmentation observed in our cohort. However, this apparent discrepancy can be explained by the presence of diffuse pigmentation on dermoscopy in 19 out of 76 tumors (25%), making it difficult ‒ or even impossible ‒ to identify specific pigmented structures (Fig. 2). Such a dense pigmentation pattern poses a diagnostic challenge, as these lesions may mimic blue nevus, melanoma, or vascular tumors. The dense pigment, often lacking recognizable dermoscopic architecture, also hinders visualization of non-pigmented structures.

Prevalence of pigmented dermoscopic structures in basal cell carcinoma: comparison with a systematic review.10

Differences between the more prevalent dermoscopic structures in nodular and superficial BCCs were identified, corroborating previous studies.10 Nodular BCCs had large blue-grey ovoid nests and arborizing telangiectasias, whereas superficial BCCs more often presented multiple small erosions, leaf-like structures, spoke-wheel structures, and a white/red structureless background. These findings are consistent with those described by Reiter et al.,10 confirming the ability of dermoscopy to predict BCC subtype even in darker skin.
Study limitations include its retrospective design, potential selection bias due to inclusion of clinically suspicious lesions, and subjectivity in both phototype classification and dermoscopic interpretation. To minimize these biases, three dermatologists jointly evaluated all images and reached a consensus.
In conclusion, most BCCs in phototypes IV and V are pigmented, often diffusely, which may mask classical diagnostic features. Leaf-like areas represent the most frequent dermoscopic structure, whereas vascular patterns are less visible. Recognizing these distinctive features is essential to improve diagnostic accuracy in skin of color. Expanding research to include more diverse populations will help refine dermoscopic criteria and promote greater equity in dermatologic care.
Authors' contributionsPriscila Jordana Costa Valadares: Critical literature review; data collection, analysis and interpretation; preparation and writing of the manuscript; study conception and planning.
Maria Luisa Pires de Freitas: Data collection, analysis and interpretation.
Diego Guimarães Florêncio Pujoni: Statistical analysis.
Flávia Vasques Bittencourt: Data collection, analysis and interpretation; effective participation in research orientation; manuscript critical review; study conception and planning.
Ethics statementUniversidade Federal de Minas Gerais IRB approval #5137559.
Financial supportNone declared.
Research data availabilityThe entire dataset supporting the results of this study was published in this article.
None declared.
Study conducted at the Dermatology Service, Hospital das Clínicas, Universidade Federal de Minas Gerais, Belo Horizonte, MG, Brazil.


