



Polycaprolactone (PCL) injectable fillers, such as Ellansé®️, are widely used in aesthetic medicine to stimulate collagen production through controlled inflammation.1 Although generally considered safe, adverse events have been reported in approximately 4.5% of treated patients.2 However, the true incidence may be underestimated, as complications are not consistently reported in the literature. In susceptible individuals, particularly those with autoimmune or granulomatous conditions, PCL can trigger persistent foreign body granulomas that are notoriously difficult to treat.3,4 We report a case of refractory PCL-induced granulomas in a patient with ankylosing spondylitis and pulmonary sarcoidosis, successfully managed with tofacitinib, a Janus Kinase (JAK) 1/3 inhibitor, suggesting a novel off-label therapy.
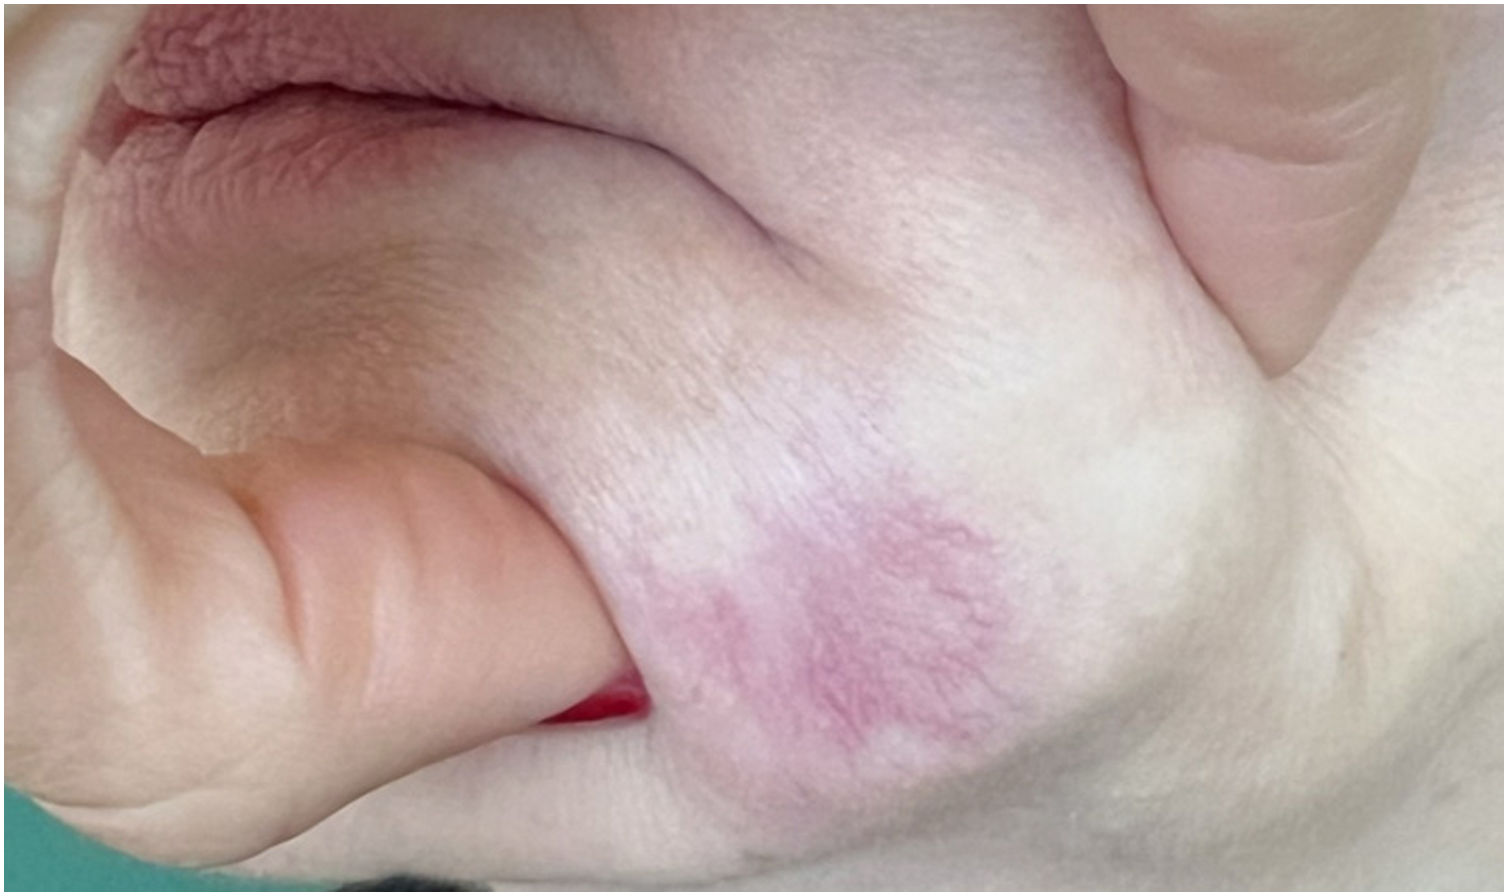
A 59-year-old woman with ankylosing spondylitis, treated with certolizumab pegol (200 mg/mL subcutaneously every 15-days), and a history of pulmonary sarcoidosis underwent facial bio-stimulation with Ellansé®️ in October 2021, performed by a dental surgeon. Eight months later, in June 2022, she developed facial edema and multiple firm nodules in the nasolabial and labiomental folds, and in the zygomatic and mandibular regions; some of them were associated with telangiectasia (Fig. 1). Initial treatment with intralesional corticosteroids, hyaluronidase, and saline injections yielded minimal improvement.5

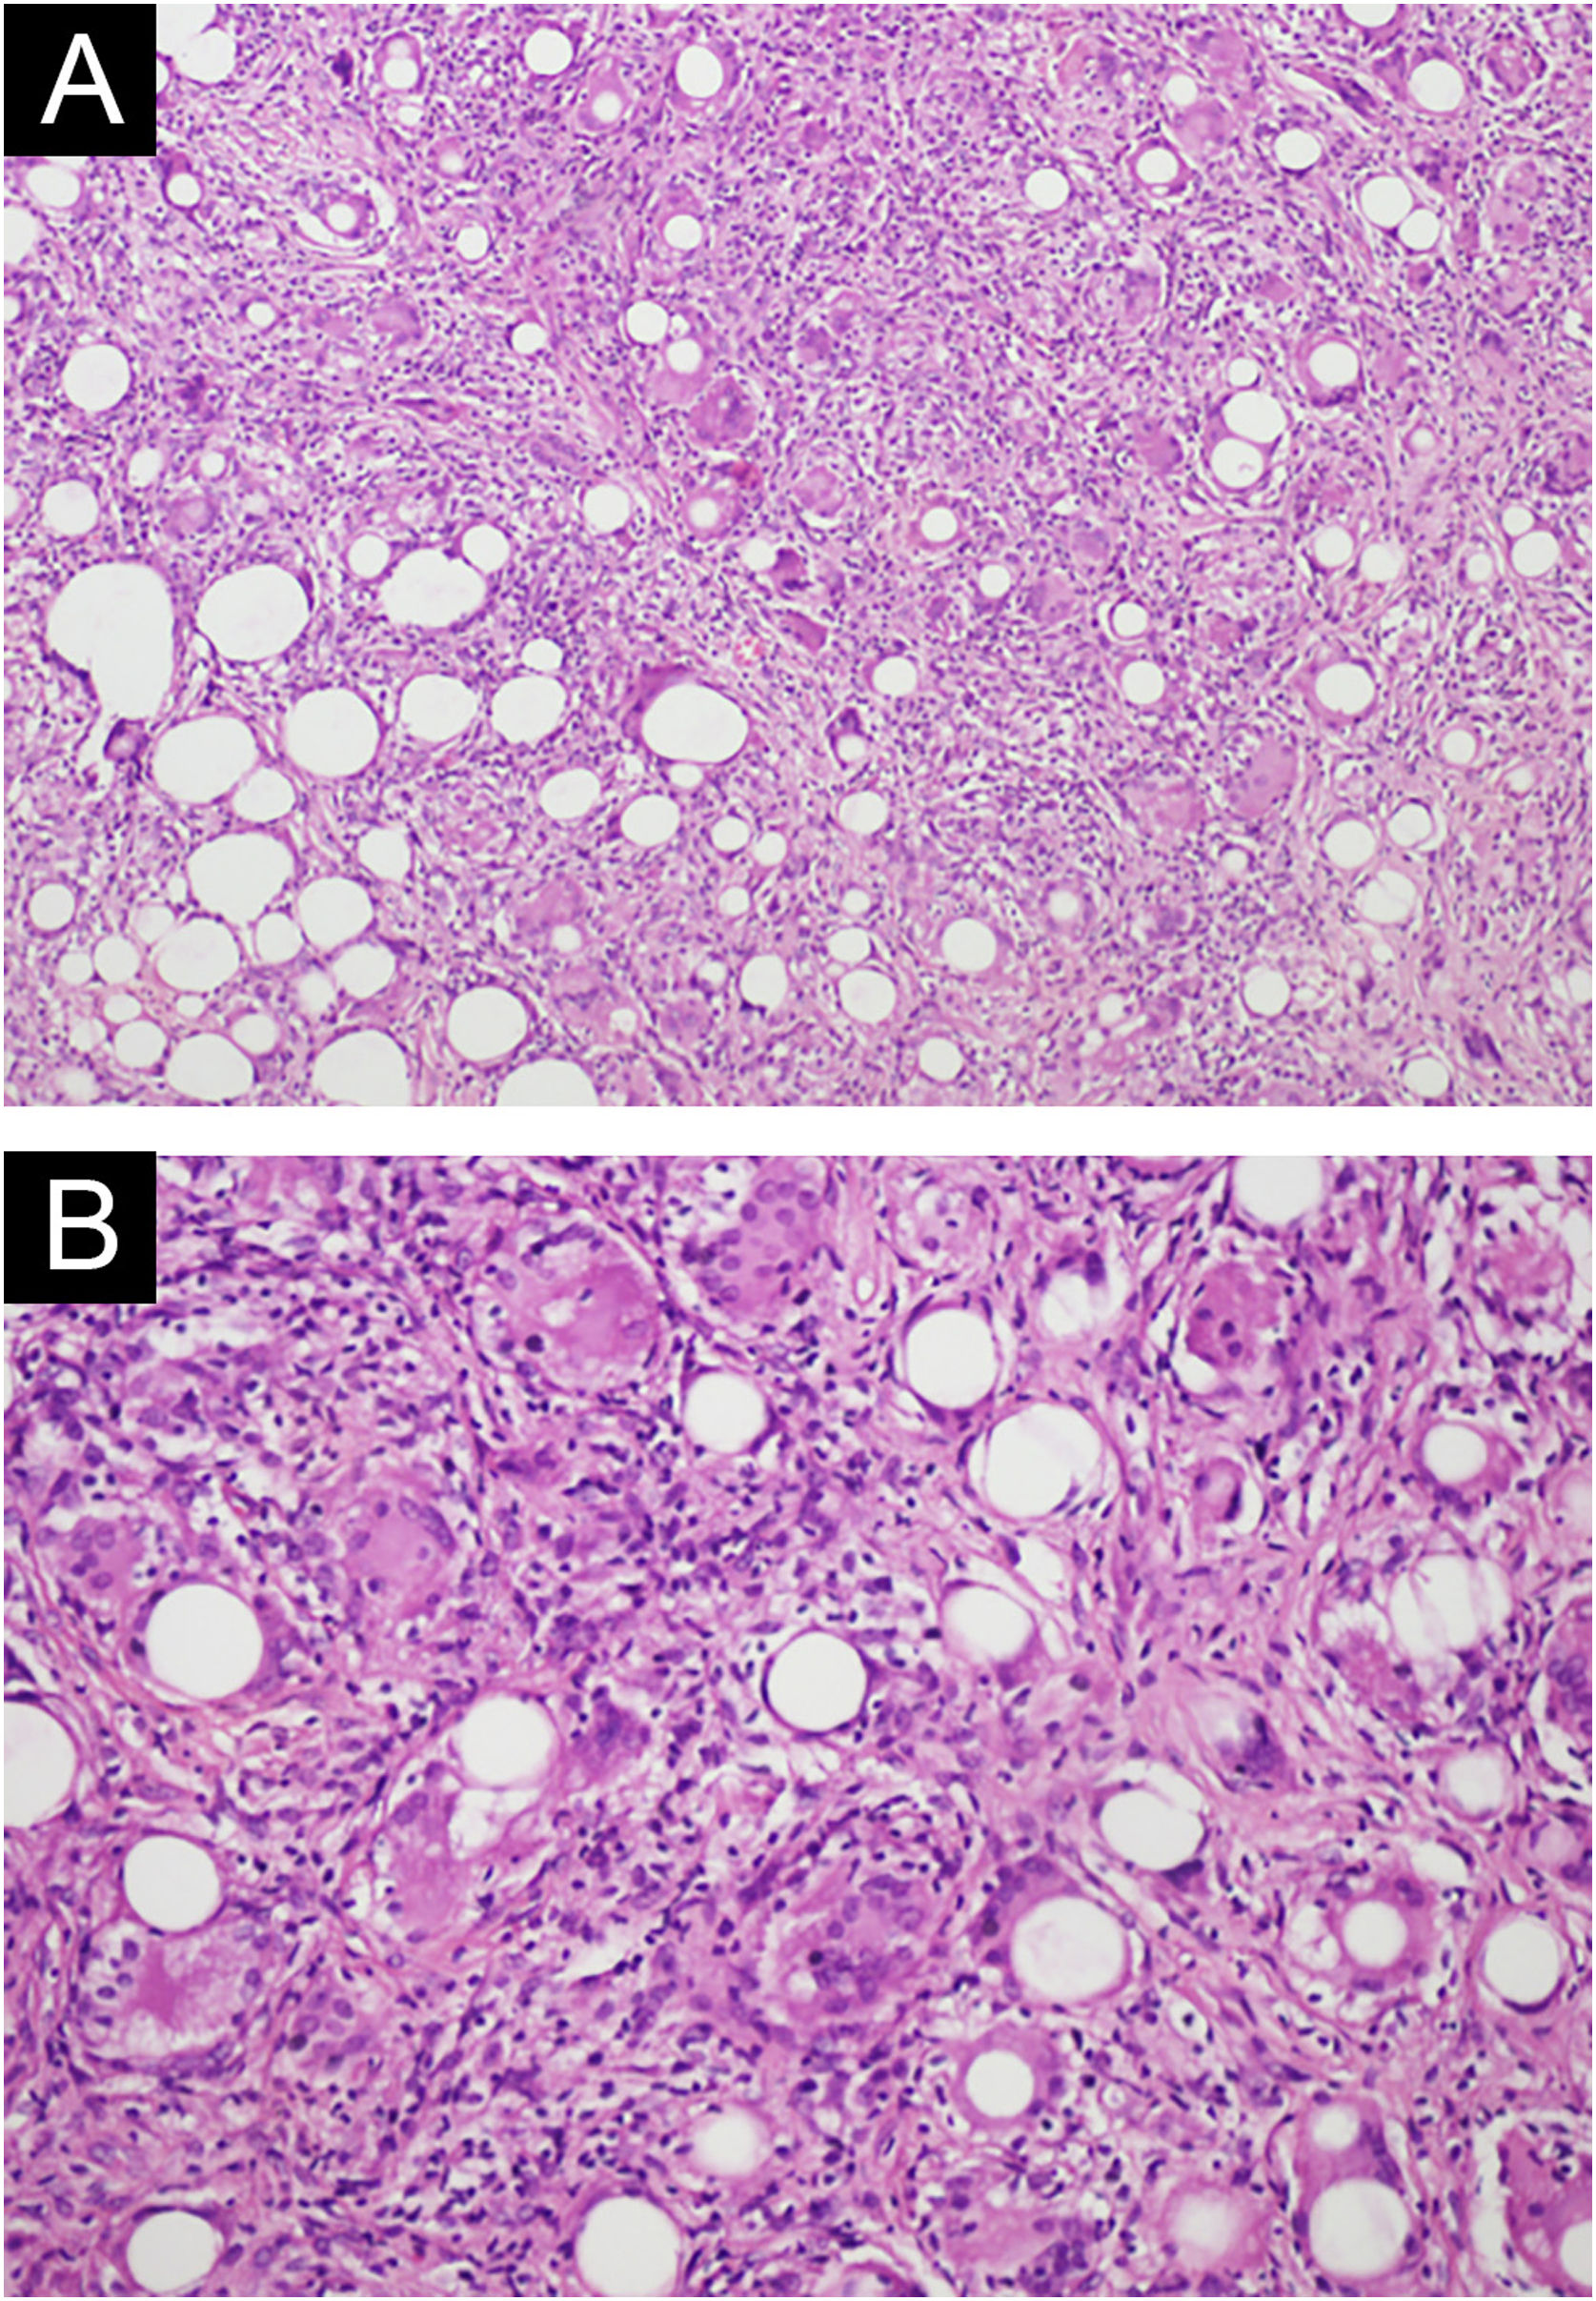
In early 2023, the patient reported dyspnea and new painful nodules on her index fingers and plantar surfaces. Chest computed tomography revealed bilateral hilar and mediastinal lymphadenopathy with perilymphatic distribution, consistent with her known pulmonary sarcoidosis. Biopsies confirmed cutaneous sarcoidosis in the finger and plantar nodules and a foreign body granulomatous reaction to PCL microspheres in a facial nodule (Fig. 2A and B). Oral prednisone (40 mg/day) improved the facial nodules, but recurrence occurred upon tapering.

(A) Histological findings of diffuse nodular inflammatory infiltrate composed of foreign body-type giant cells containing single regular microspheres within their cytoplasm, interspersed with macrophages, lymphocytes, and fibroblasts. Hematoxylin and eosin, 100×. (B) Higher magnification of the granuloma showing microspheres with similar diameters. Hematoxylin & eosin, 200×.
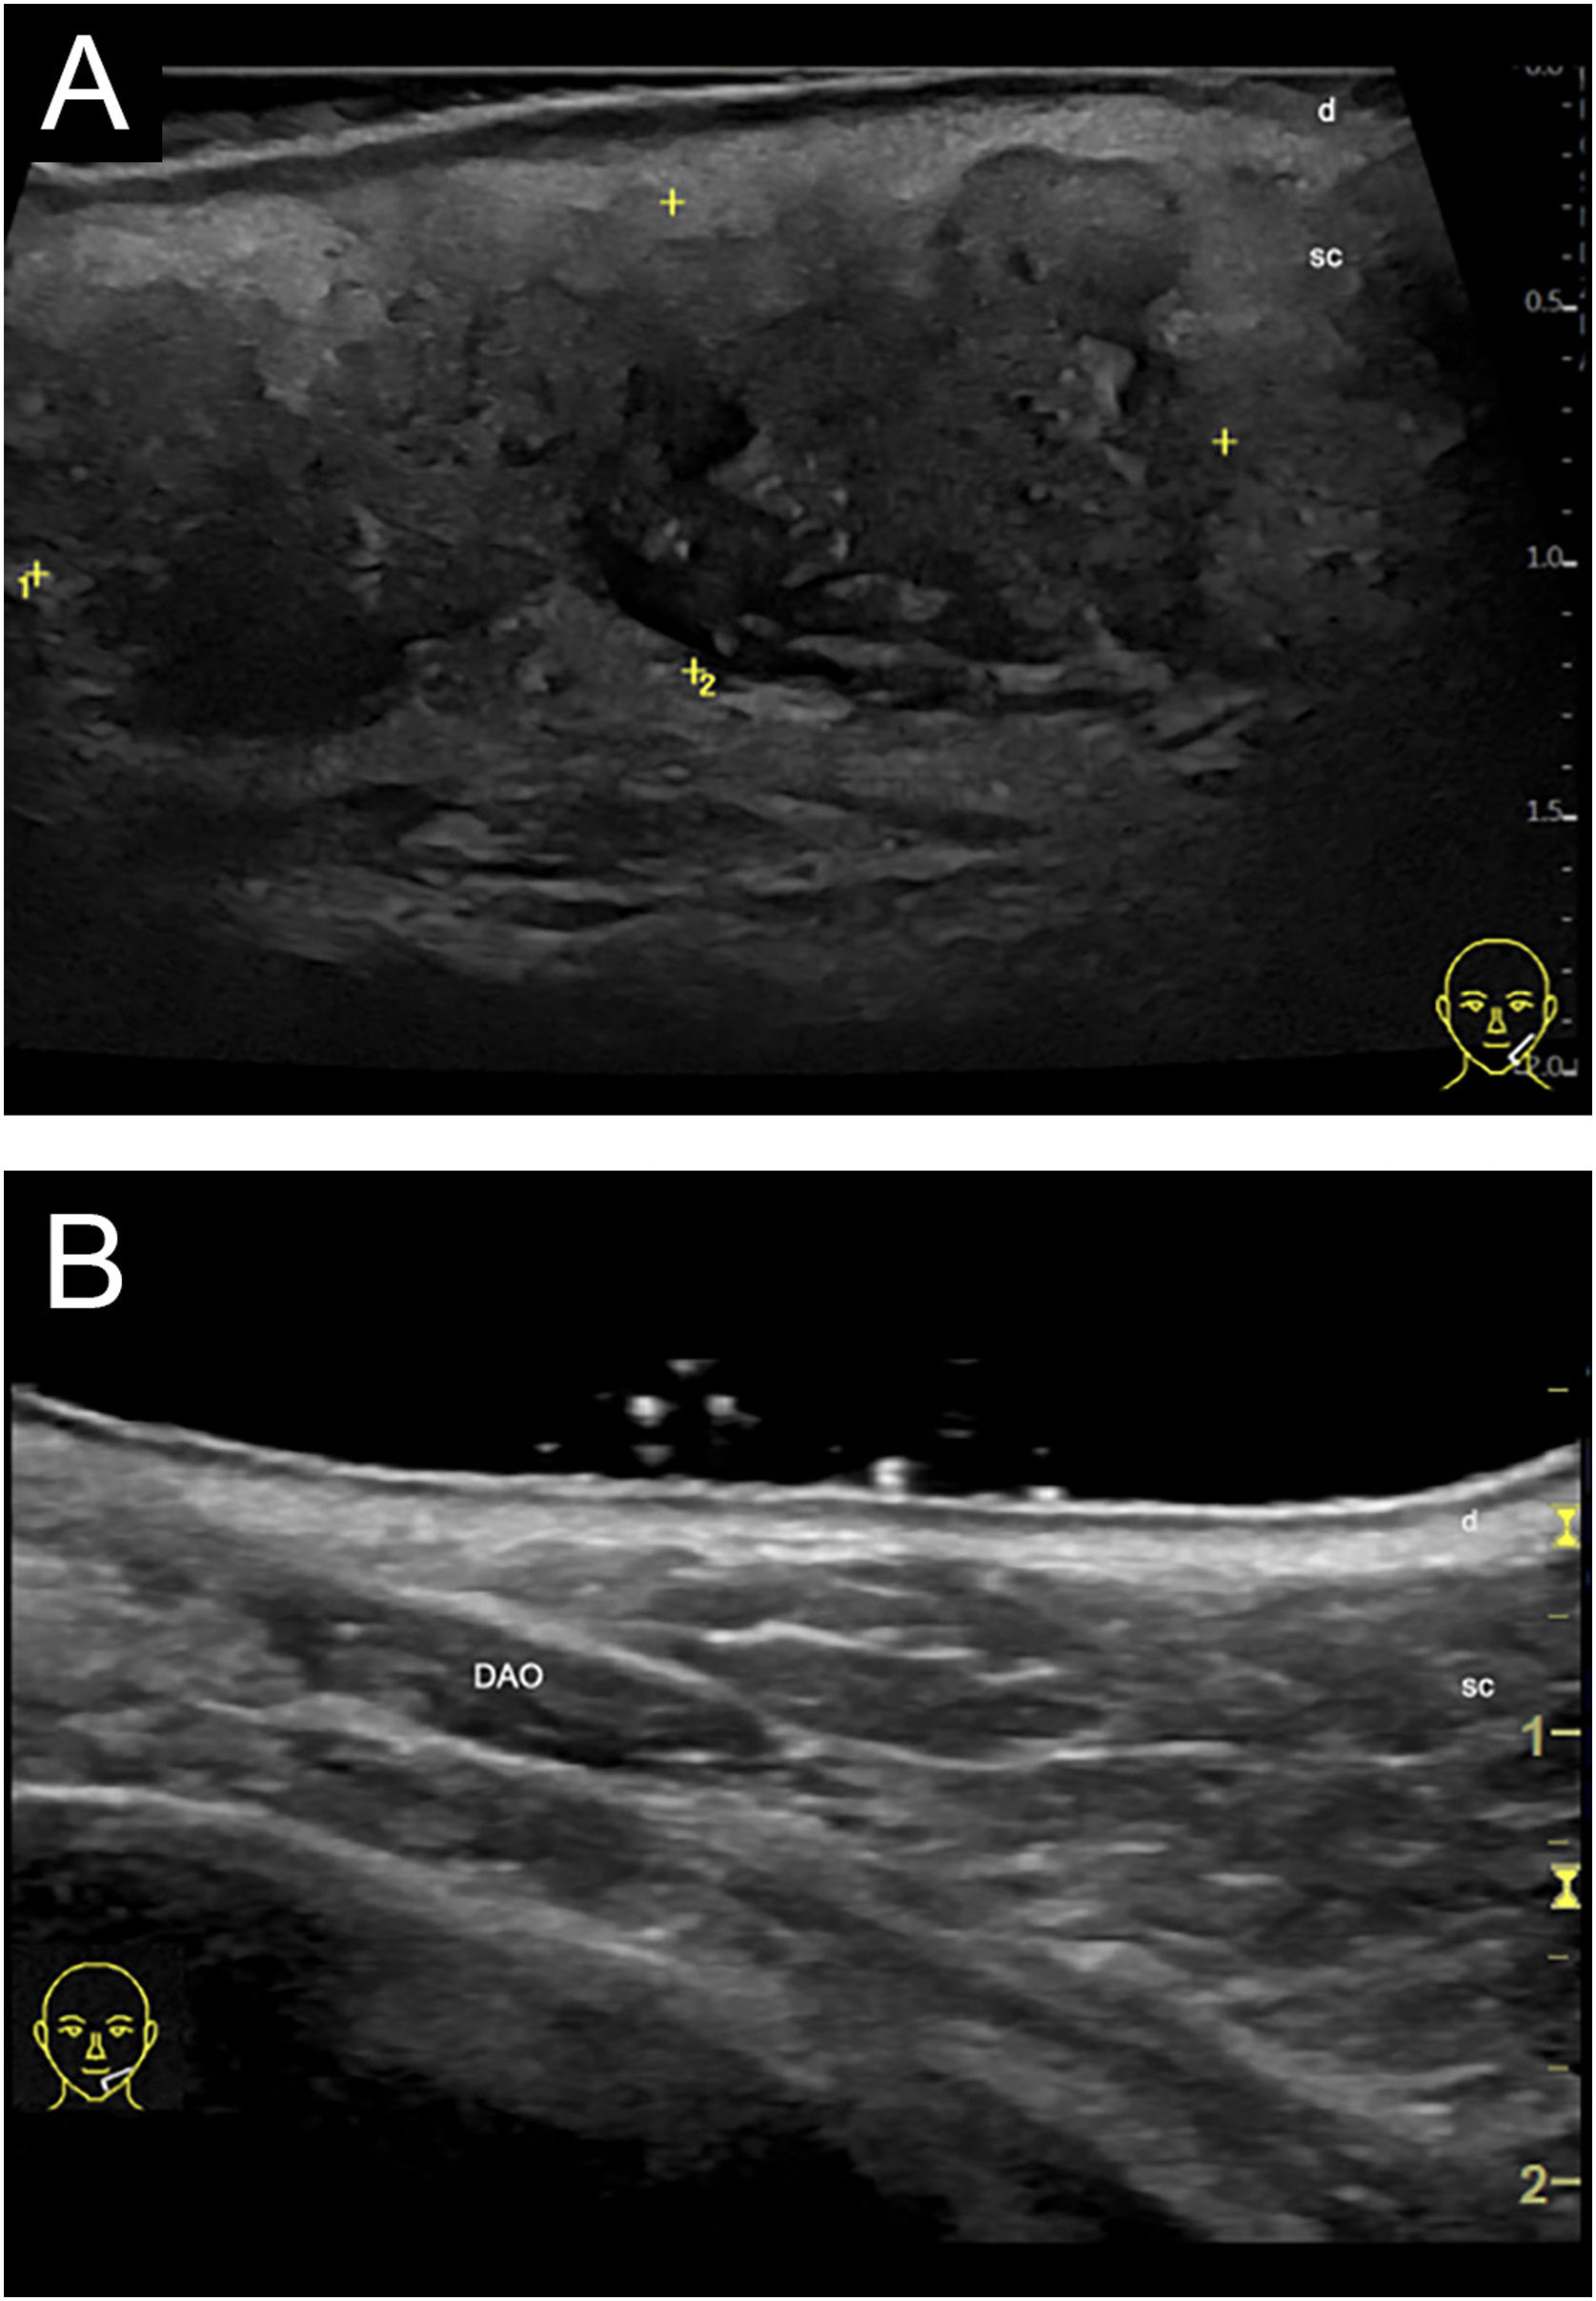
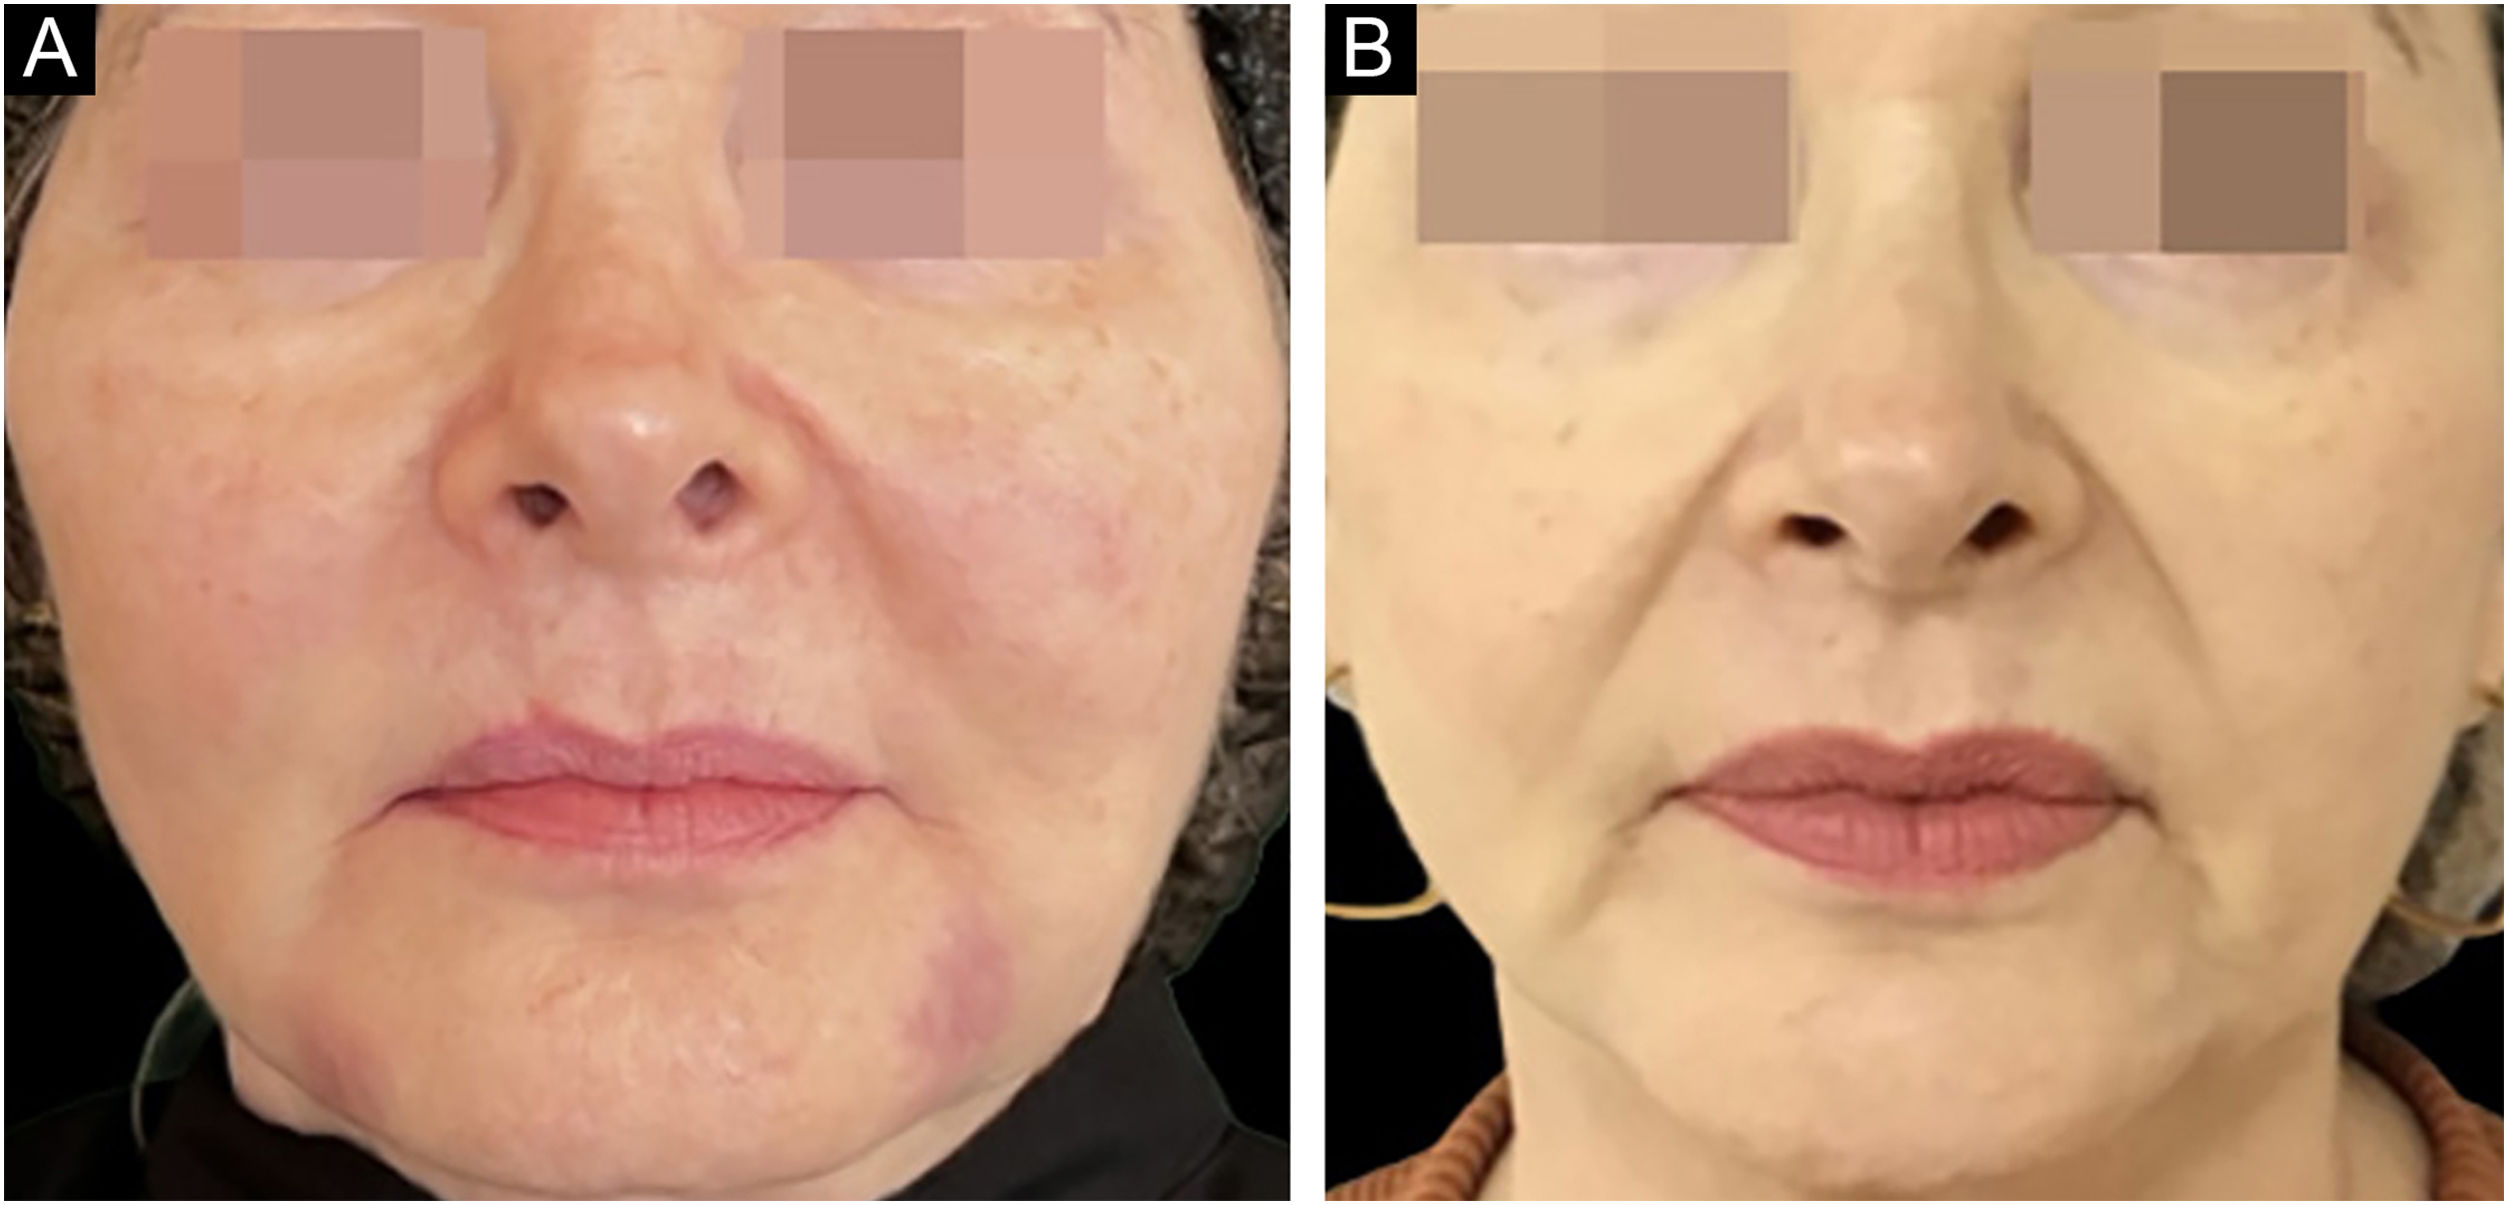
In July 2024, high-frequency dermatologic ultrasound revealed multiple lobulated, hypoechoic nodules, with some hyperechoic foci and comet tail artifact, in the subdermal, subcutaneous, and muscular planes (Fig. 3A), with peripheral vascularization on color Doppler, alongside enlarged, heterogeneous lacrimal glands with increased vascularity. Given the refractory granulomas and complex medical history, tofacitinib 5 mg twice daily was initiated. Within weeks, the patient experienced near-complete resolution of facial (Fig. 3B) and sarcoidal nodules, sustained at 1-year follow-up (Fig. 4A and B). The patient is still receiving tofacitinib due to the diagnosis of ankylosing spondylitis.

Polycaprolactone-Induced Granuloma. High-frequency ultrasound images of the mandibular region showing (A) an ill-defined hypoechoic nodule (between yellow markers) affecting the dermis (d), subcutaneous tissue (sc) and the DAO (depressor anguli oris muscle), suggestive of granulomatous reaction, and (B) Complete resolution of the nodule –1 year follow up.

PCL fillers aim to induce controlled inflammation for collagen deposition, but in patients with autoimmune diseases or granulomatous conditions like pulmonary sarcoidosis, this response can become dysregulated, leading to persistent granulomas. The coexistence of cutaneous and pulmonary sarcoidosis in this patient suggests a predisposition to granulomatous reactions, likely exacerbated by PCL. Conventional treatments, such as corticosteroids and hyaluronidase, often fail, with high recurrence rates, as seen here.6
Tofacitinib, by inhibiting JAK 1/3-mediated cytokine signaling, targets the inflammatory pathways driving granulomatous reactions.6–8 Its efficacy in this case highlights its potential as a therapeutic option for refractory PCL-induced granulomas, particularly in patients with autoimmune or granulomatous comorbidities. Although tofacitinib is not approved for sarcoidosis or filler-induced granulomas, its off-label use was ethically justified in this case of refractory sarcoidosis, supported by emerging literature demonstrating the efficacy of JAK inhibition in granulomatous diseases, with the treatment decision made jointly by the medical team and the patient after detailed discussion and informed consent. While further studies are needed to confirm safety and efficacy, this case underscores the promise of JAK inhibitors in managing such complications.
Clinicians should exercise caution when using PCL fillers in patients with autoimmune or granulomatous conditions and could consider tofacitinib for treatment-resistant granulomas. This case highlights the need for heightened awareness of PCL-related complications and the potential of JAK inhibitors as an innovative therapy.
ORCID IDsRômulo Henrique Malaquias: 0009-0005-2646-2785
Nilceo Michalany: 0000-0002-9300-163X
Carlos G. Wambier: 0000-0002-4636-4489
Samira Yarak: 0000-0002-5657-6645
Ethical approvalReviewed and approved by the Ethics Committee; Approval nº 8.135.388.
Research data availabilityDoes not apply.
Financial supportNone declared.
Authors’ contributionsRosa Maria Silveira Sigrist: Approval of the final version of the manuscript; critical literature review; data collection, analysis and interpretation; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review; preparation and writing of the manuscript; study conception and planning.
Rômulo Henrique Malaquias: Approval of the final version of the manuscript; critical literature review; data collection, analysis and interpretation; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review; preparation and writing of the manuscript; study conception and planning.
Nilceo Michalany: Approval of the final version of the manuscript; data collection, analysis and interpretation; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review.
Carlos G. Wambier: Approval of the final version of the manuscript; effective participation in research orientation; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review.
Samira Yarak: Approval of the final version of the manuscript; critical literature review; data collection, analysis and interpretation; effective participation in research orientation; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review; preparation and writing of the manuscript; study conception and planning.
None declared.
Study conducted at the Department of Dermatology, Universidade Federal de São Paulo, São Paulo, SP, Brazil.


