



Cutaneous botryomycosis is a rare chronic granulomatous bacterial infection that usually occurs in immunocompromised patients or with a history of previous trauma.1
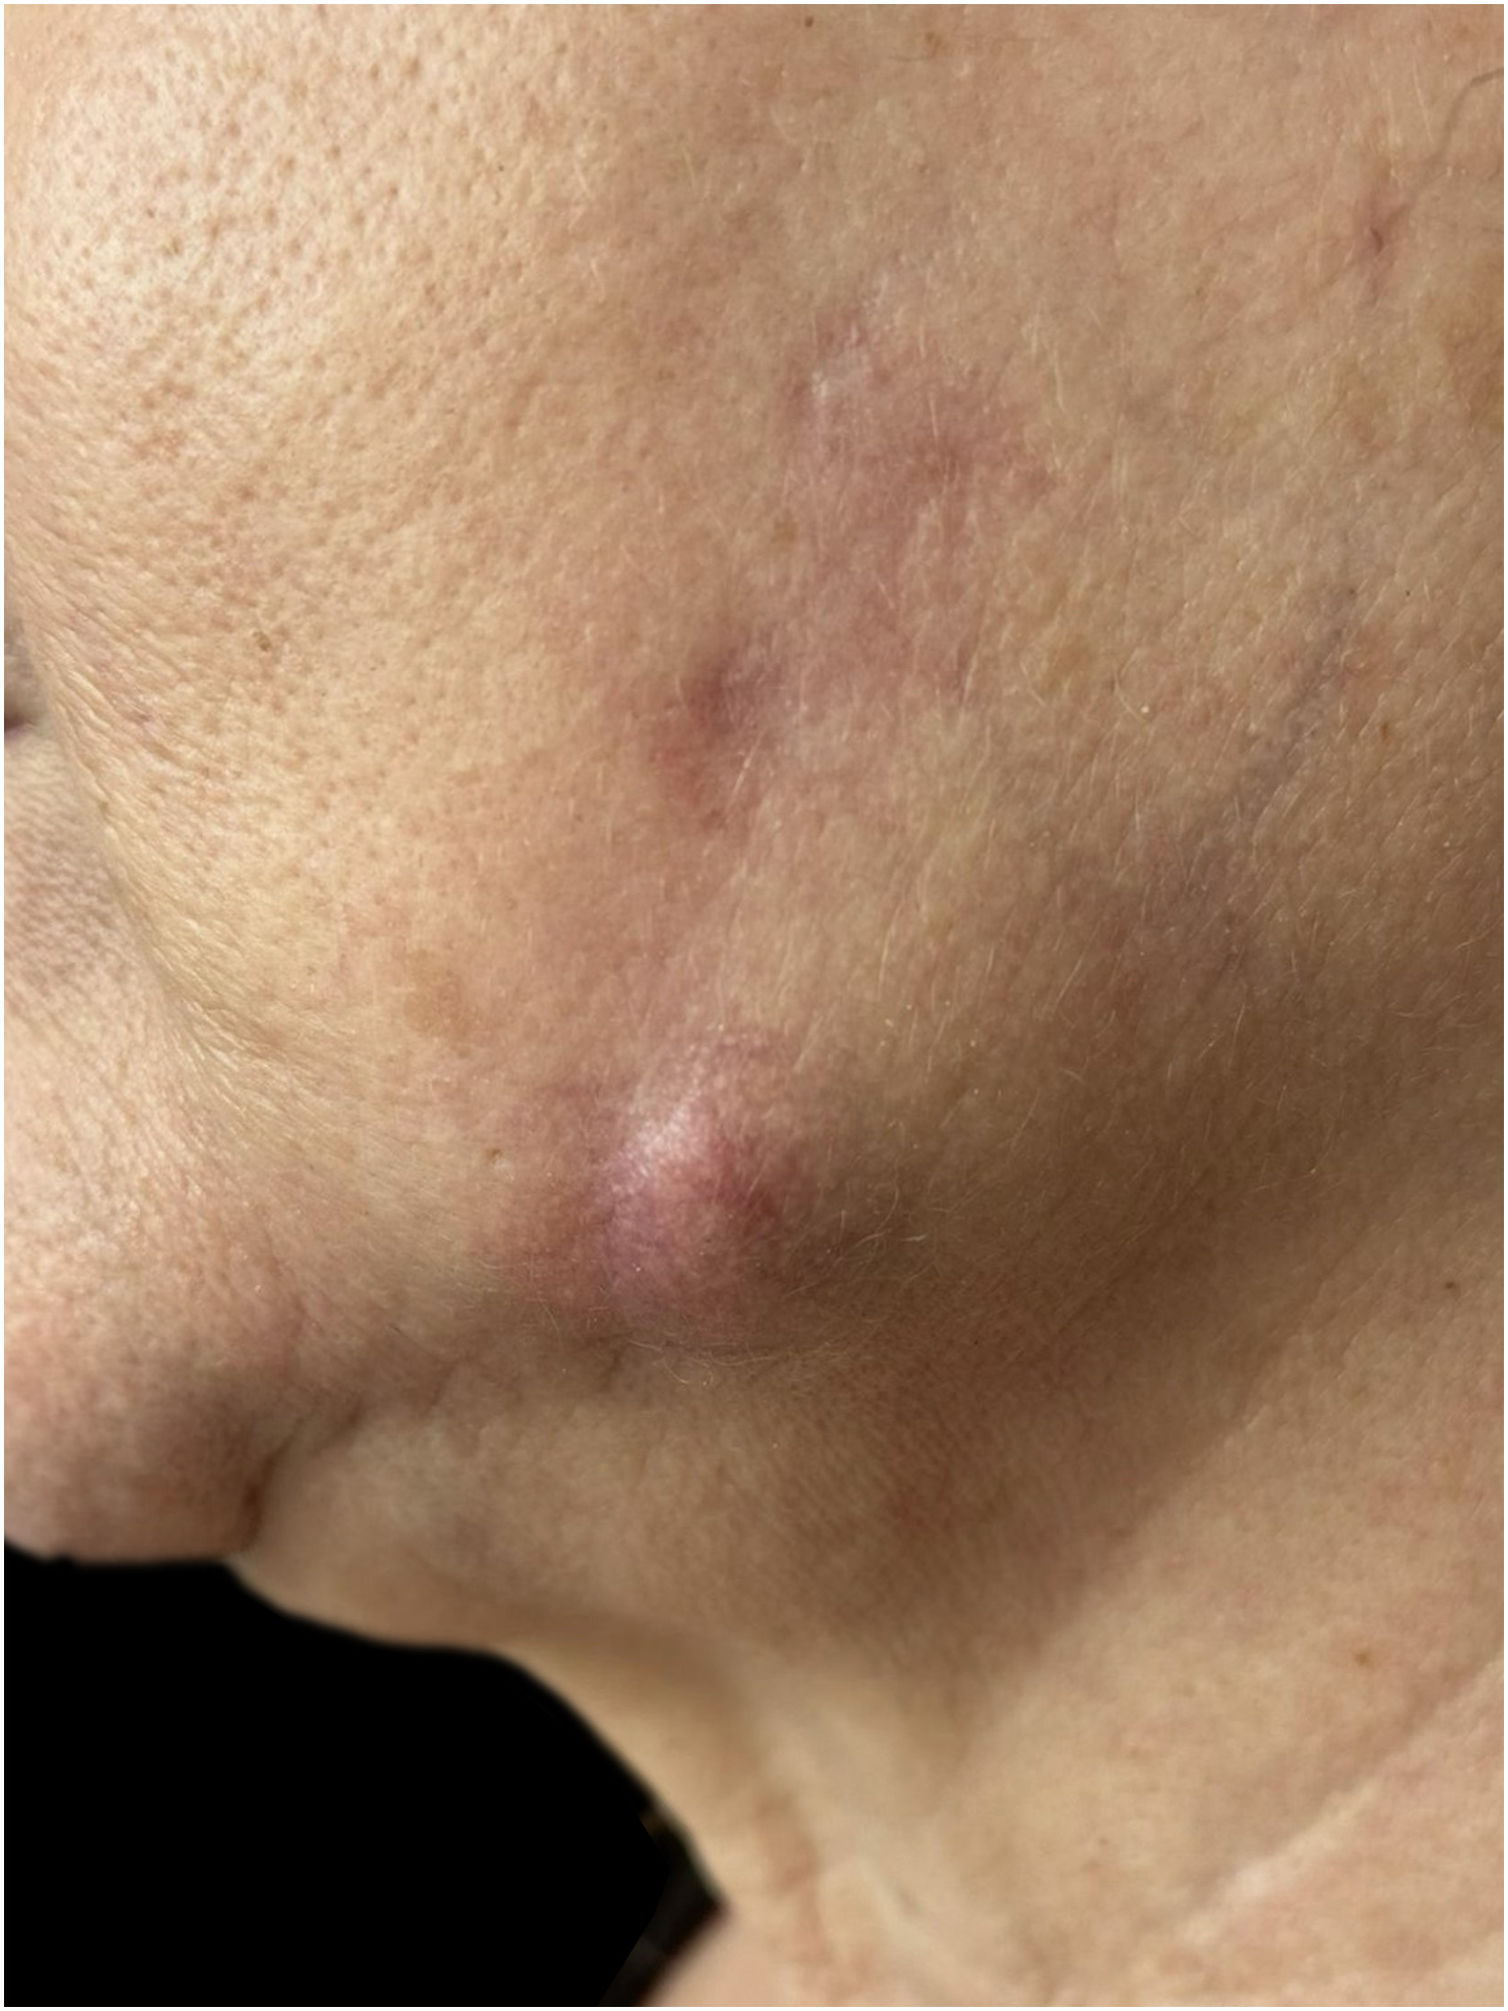
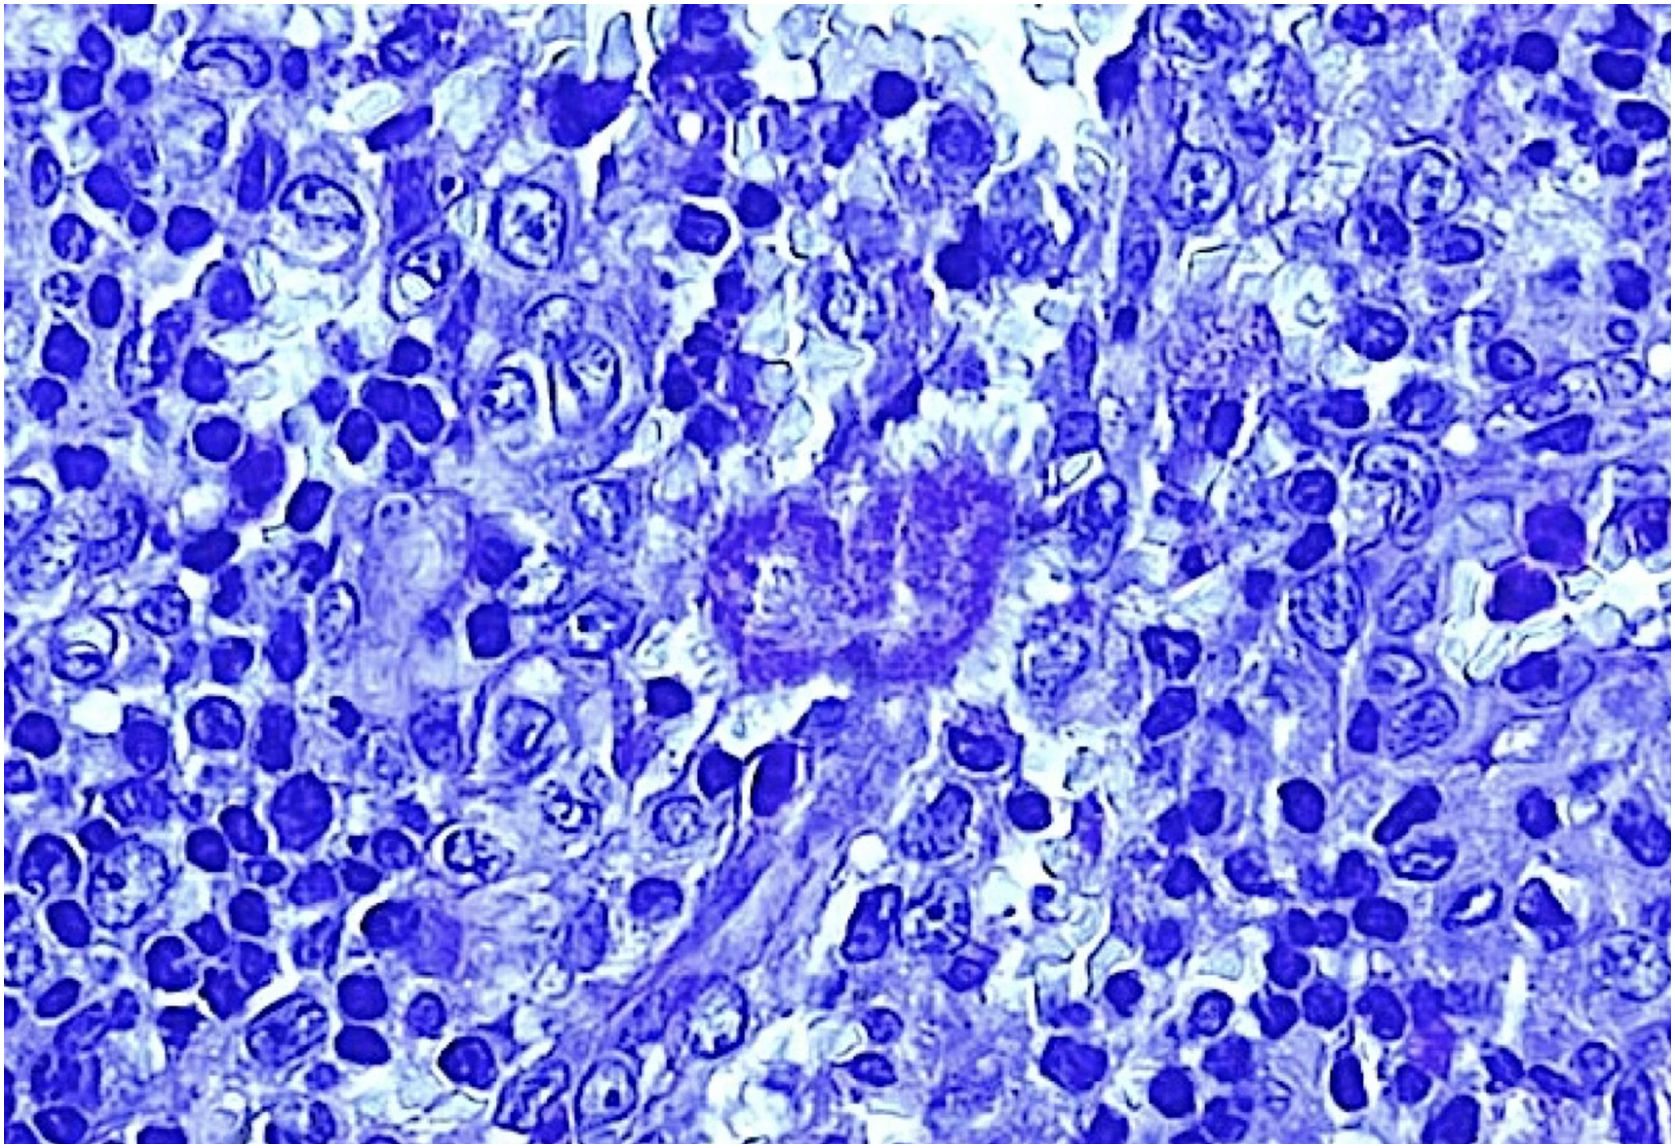
A 64-year-old woman with a history of tensor thread placement one month prior to her condition, without comorbidities. She went to a private dermatologist for dermatosis on the right mandibular region, consisting of a nodule measuring 5 × 4 cm (Fig. 1), painful to palpation, with 9-months of evolution. A spindle incisional skin biopsy was performed, which reported a dense superficial and deep inflammatory infiltrate composed of histiocytes, Langhans-type multinucleated giant cells, neutrophils, and plasma cells, with the formation of a pseudofistula. The PAS stain showed a small grain composed of multiple filamentous bacteria (Fig. 2). Gram stain was negative. Molecular biology was performed, showing Klebsiella michiganensis. With the above, botryomycosis was diagnosed. The patient was treated with ciprofloxacin orally (500 mg every 12-hs) for three months, with complete remission.


Cutaneous botryomycosis has an insidious onset. The extremities are the most affected, while the head and neck are less frequently involved. It manifests with nodules, abscesses, fistulas, and ulcers with seropurulent discharge, which may have yellow grains like those of actinomycosis.1
Accidental or postoperative skin trauma favors this infection.2 In this patient, the placement of tensor threads was the source of trauma and bacterial inoculation.
The granules in botryomycosis are basophilic, positive to Periodic acid-Schiff (PAS) stain, and may be detectable or not by Gram staining, depending on the causative agent.3
It must be differentiated from other diseases that produce papules, such as mycetoma, actinomycosis, and nocardiosis.4 Histopathology, culture, and molecular biology are helpful to make this distinction.3,5
The most frequent etiologic agent is Staphylococcus aureus, followed by Pseudomonas aeruginosa. Other causative microorganisms are Escherichia coli, coagulase-negative staphylococci, Streptococcus spp., and Proteus spp.6 The isolation of Klebsiella michiganensis in this case is exceptional. Diagnostic confirmation required integrating clinical, histopathological, and molecular findings, using sequencing and RT-PCR targeting specific regions of the 16S rRNA gene, thereby confirming the diagnosis.
Klebsiella michiganensis (mi.chi.ga.nen.sis. NL adj. masc. michiganensis, from or belonging to the state of Michigan, USA, where the strain was isolated) is a bacterium first described in 2013, as one of the nine species of the K. oxytica complex within the genus Klebsiella. It is characterized by the formation of small, circular, mucoid, convex, entire, opaque, and white colonies. The cells are straight bacilli, gram-negative, encapsulated, immobile, 0.5–0.8 μm in diameter and 1.0–2.0 μm in length, with facultative anaerobic metabolism.5
Treatment of botryomycosis is based on susceptibility-targeted antibiotics until the infection resolves. The ability of K. michiganensis to acquire and disseminate antimicrobial resistance genes is a matter of growing concern. Carbapenemase-producing strains, such as OXA-181 and NDM-1, have been reported to be associated with motile plasmids such as IncHI5 and IncFIB,4,6 which present multiresistance to β-lactams, aminoglycosides, fluoroquinolones, and sulfonamides.4 In our case, antibiotic resistance tests were performed, including the detection of genes such as blaKPC, NDM, or OXA, without finding mechanisms of resistance to fluoroquinolones in our strain, which explains the good clinical response to ciprofloxacin.
The present case constitutes the first report of cutaneous botryomycosis secondary to an aesthetic procedure caused by Klebsiella michiganensis, which broadens the etiological spectrum of this entity. Precise identification using molecular techniques was fundamental for diagnosis, highlighting the limitations of conventional methods for recently described species.
ORCID IDsMartha Daniela Alcázar Olaiz: 0000-0001-6512-2322
Roberto Arenas Guzmán: 0000-0002-2992-9564
Rigoberto Hernández Castro: 0000-0002-5656-0942
Grecia Figueroa Ramos: 0000-0003-2068-6911
Research data availabilityDoes not apply.
Financial supportNone declared.
Authors’ contributionsSamantha Cruz López: Approval of the final version of the manuscript; critical literature review; preparation and writing of the manuscript.
Martha Daniela Alcázar Olaiz: Approval of the final version of the manuscript; critical literature review; preparation and writing of the manuscript.
Carlos Daniel Sánchez Cárdenas: Approval of the final version of the manuscript; preparation and writing of the manuscript.
Roberto Arenas Guzmán: Approval of the final version of the manuscript; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review.
Rigoberto Hernández Castro: Approval of the final version of the manuscript; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review.
Grecia Figueroa Ramos: Approval of the final version of the manuscript; intellectual participation in propaedeutic and/or therapeutic management of studied cases; manuscript critical review.
None declared.
Study conducted at the Hospital General “Dr Manuel Gea González”.


