



Cutaneous mucormycosis (formerly zygomycosis) is a life-threatening fungal disease that occurs when fungi of the order Mucorales penetrate the skin through a disrupted barrier. Common portals of entry include traumatic wounds, surgical sites, burns, and injection points.1 Alternatively, the disease can manifest as a secondary form following hematogenous dissemination from a primary infection at another site, which typically affects immunocompromised individuals.2 Secondary cutaneous mucormycosis may also result from a rhinocerebral infection, which typically presents with an acute onset and is associated with high mortality. Rhinocerebral infection most commonly occurs in patients with underlying conditions that favor immunosuppression, with diabetes mellitus being the most prevalent. Of note, recent observations suggest that COVID-19 patients with diabetes mellitus may represent a high-risk population for the development of rhino-orbito-cerebral mucormycosis.3 Here, we report a case of localized primary cutaneous mucormycosis without a significant history of trauma in a patient with Waldenström macroglobulinemia.
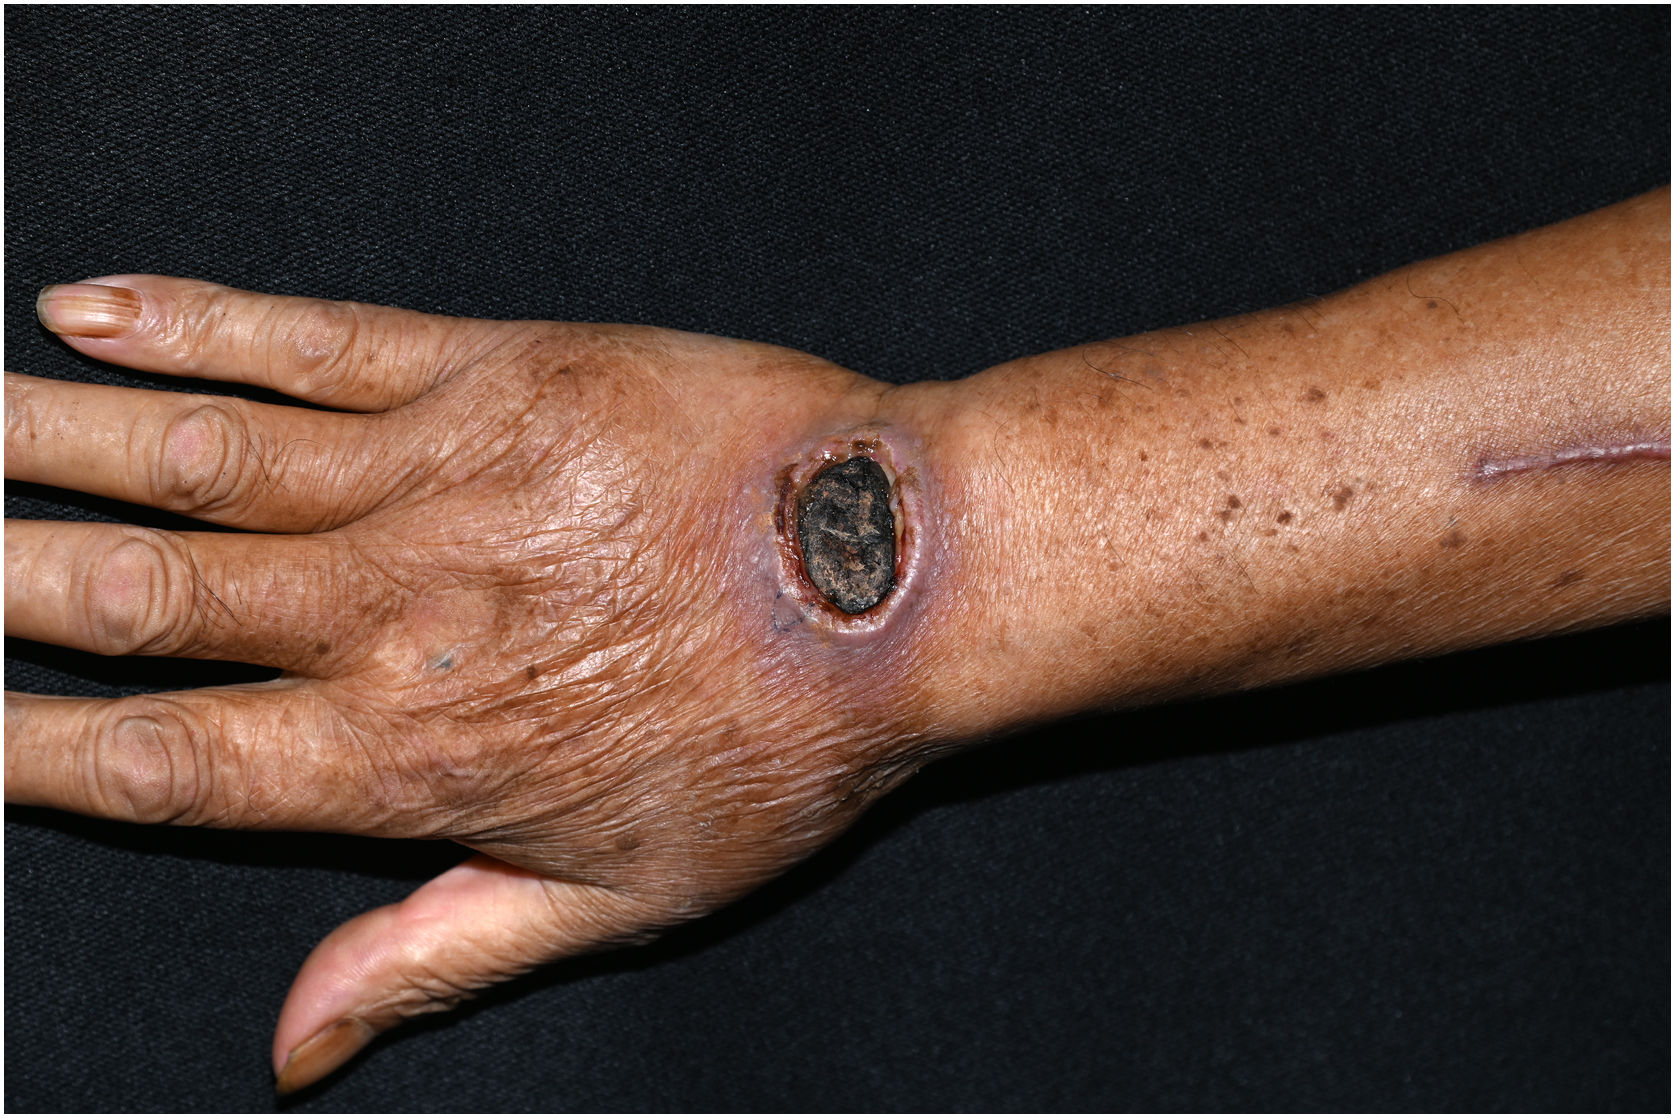
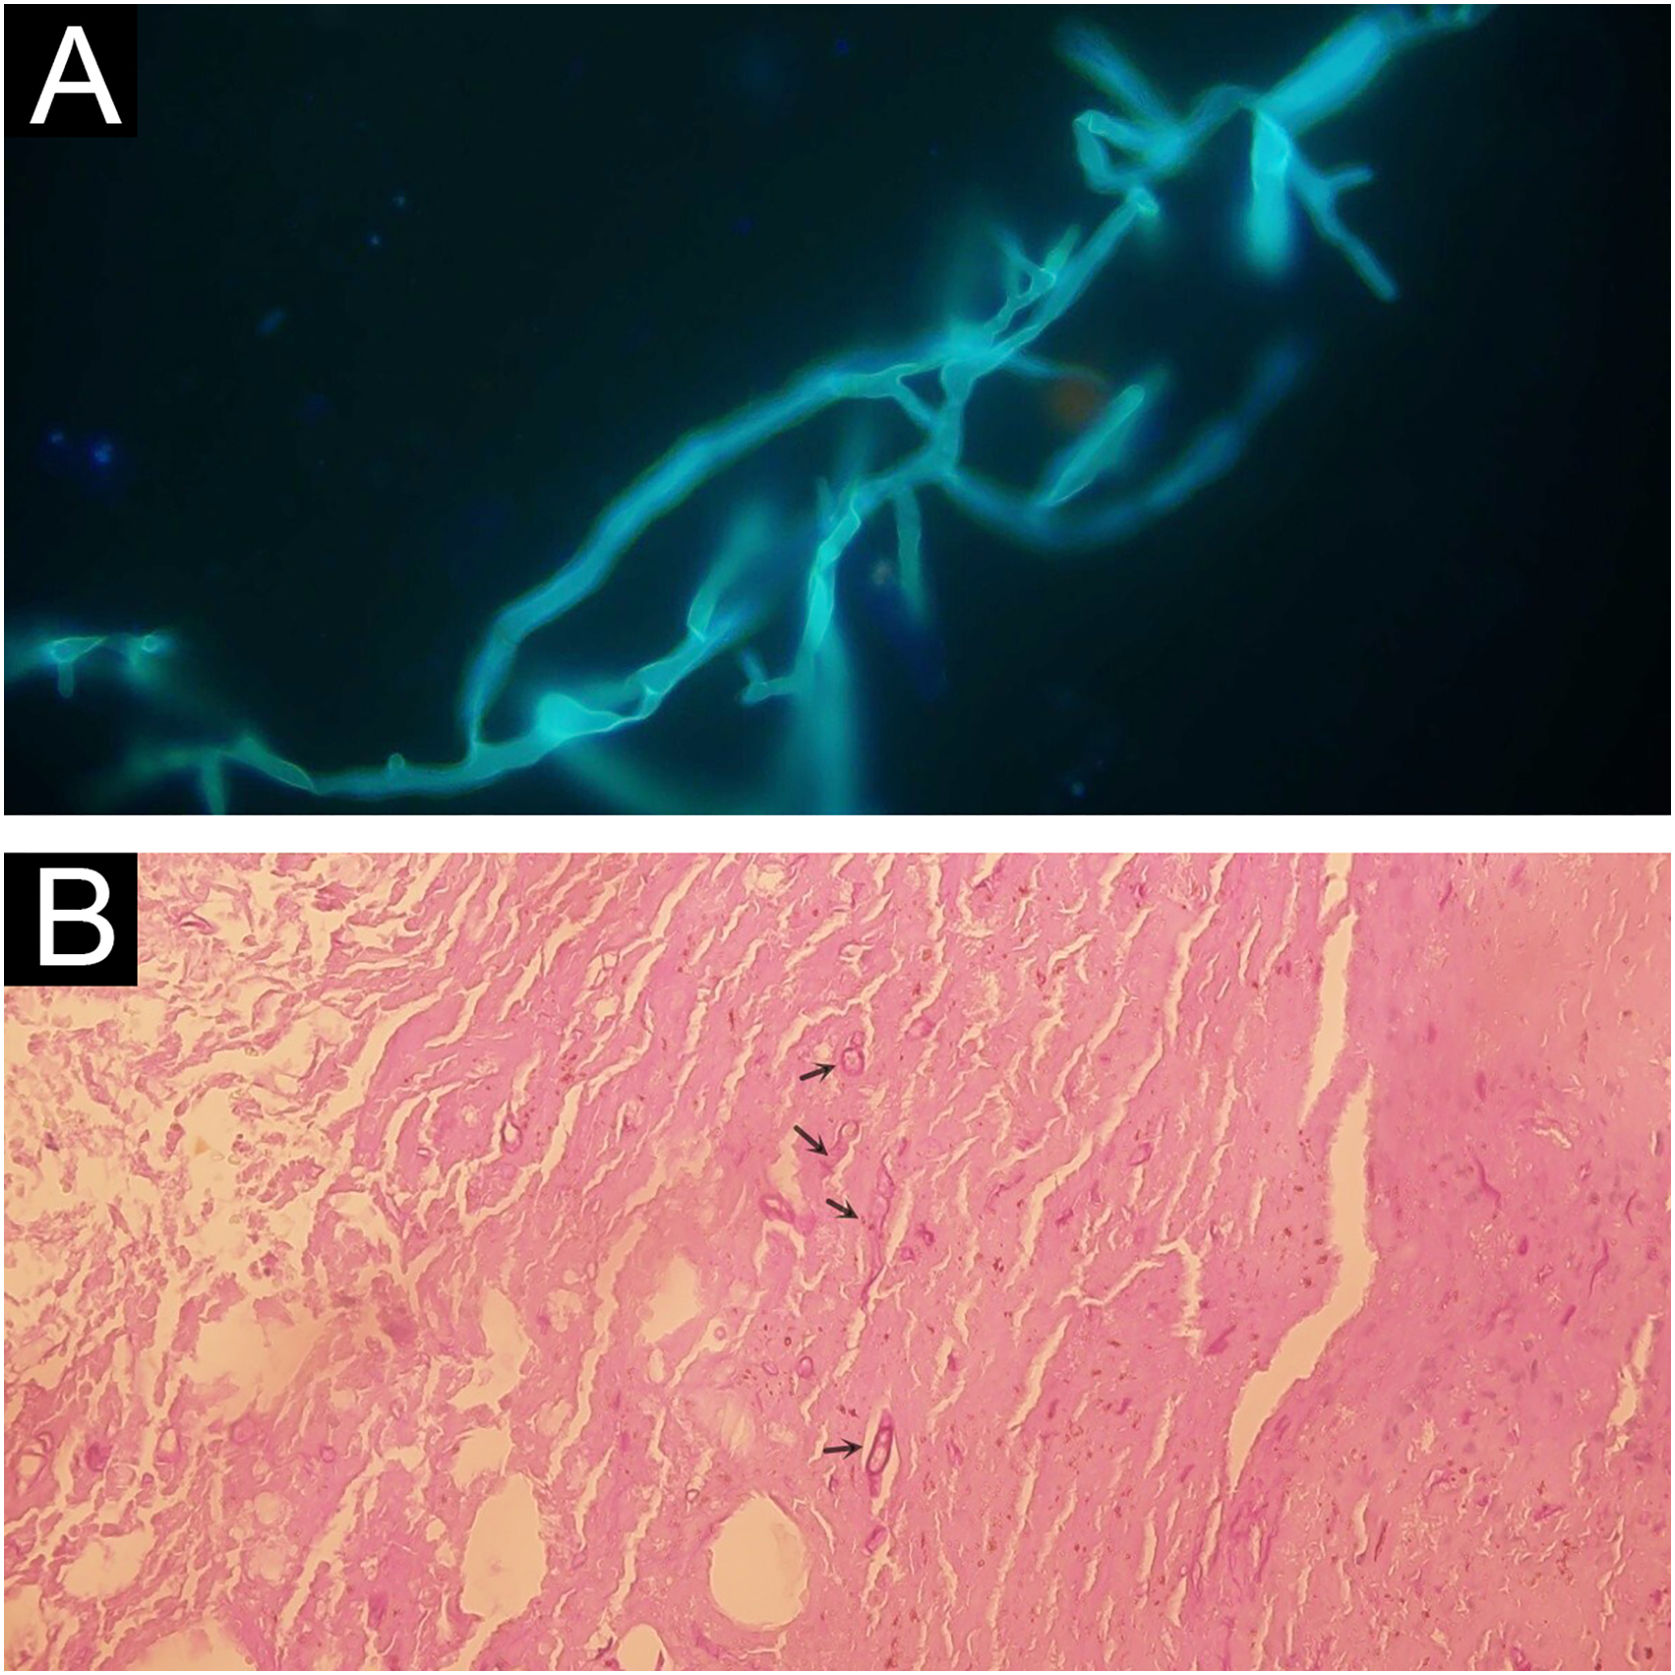
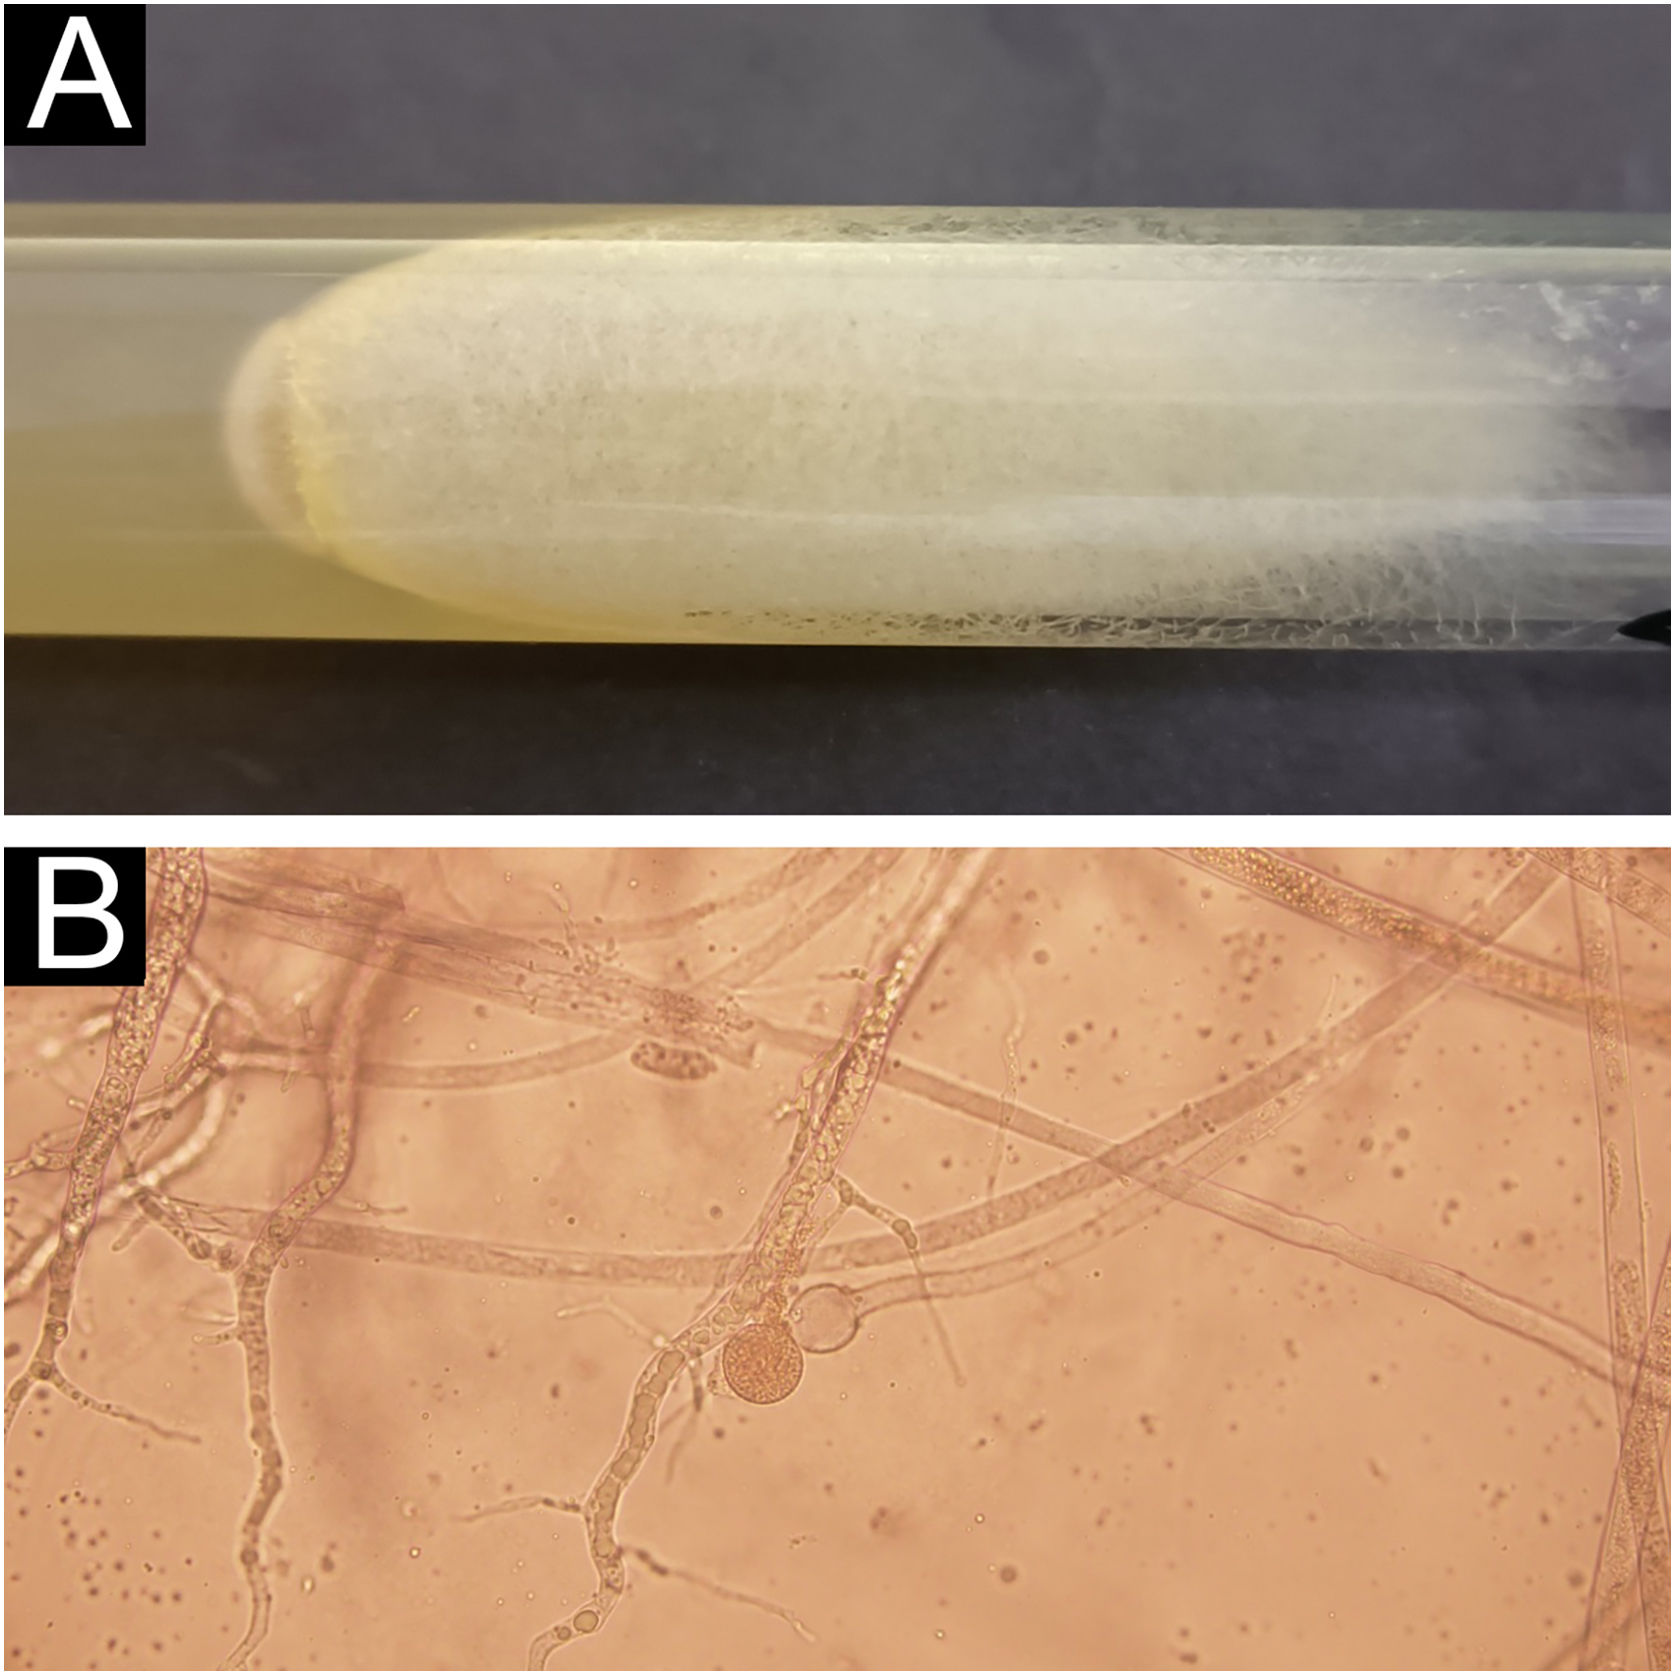
A 74-year-old male patient presented to our dermatology clinic with a gradually enlarging, mildly painful ulcerative lesion on the dorsal aspect of his right hand, which had been present for two months. The patient denied any history of trauma. His past medical history was significant for hypertension and Waldenström macroglobulinemia. He was previously treated with ibrutinib (420 mg/day) and subsequently with zanubrutinib (320 mg/day) for approximately one year. He is currently participating in a venetoclax clinical trial (HZQ1070) at another hospital, of unspecified dosage. The patient was afebrile. Laboratory tests revealed monocytosis (16.5%, normal range: 3.0%–10.0%) and elevated CRP (125.3 mg/L, normal range: 0.0–10.0 mg/L). Other blood tests were unremarkable, and the X-Ray of the hand showed no abnormalities. Dermatological examination showed a 6 × 6 cm ulcer on the dorsum of the right hand near the wrist, with a central eschar that was mobile upon palpation and raised edges surrounding the ulcer (Fig. 1), which emitted a faint putrid odor. The remainder of the physical examination was unremarkable. Scraping of the exudate from between the eschar and the raised border was performed for calcofluor white staining (CFW), which revealed numerous broad, ribbon-like hyphae of variable width, partially folded and sparsely septate under microscopy (Fig. 2A). Histopathological examination revealed hyperkeratosis, ulceration, and papillomatous epidermal hyperplasia, with dense infiltration of lymphocytes, histiocytes, neutrophils, and multinucleated giant cells in the dermis, accompanied by hemorrhage and hemosiderin deposition, and the presence of a large number of irregular hyphae in the dermis layer demonstrated by periodic acid-Schiff (PAS) stain (Fig. 2B). The exudate and tissue specimens were inoculated onto Sabouraud dextrose agar and incubated at 25 °C. After 5-days of incubation, mold colonies were observed, with abundant light yellowish aerial mycelia covering the slant, and the isolate was identified as Mucor irregularis (Fig. 3A through B) by ITS sequencing (GenBank accession nºPX566649). The diagnosis of cutaneous mucormycosis was made. The patient was prescribed oral itraconazole at a dose of 200 mg daily. After three months of treatment, the skin lesion showed marked improvement, and the patient remains under ongoing therapy.


Human pathogenic species within the order Mucorales include 27 species across 11 genera; these fungi are ubiquitous in the environment. Among these, Rhizopus is the most common genus associated with mucormycosis worldwide, with Lichtheimia (formerly Absidia), Rhizomucor, Mucor, Apophysomyces, Cunninghamella, and Saksenaea being other clinically significant genera.4M. irregularis (formerly known as Rhizomucor variabilis) is primarily found in soil and decaying fruits and vegetables. Although this pathogen has a worldwide distribution, it is most commonly reported in China.5 These fungi exhibit a prominent tendency to invade blood vessels, resulting in vascular obstruction, infarction, and ultimately, tissue necrosis. This necrosis represents a critical diagnostic feature of mucormycosis.6
Cutaneous mucormycosis often progresses rapidly owing to the propensity of Mucorales for angioinvasion, making early identification critical for the prompt initiation of antifungal therapy.7 The definitive diagnosis of cutaneous mucormycosis typically relies on histopathological examination and fungal culture. The histopathologic hallmark is the presence of broad, ribbon-like hyphae exhibiting right-angled branching.8 Direct microscopic examination of potassium hydroxide (KOH) preparations or calcofluor white staining can facilitate early detection, typically revealing broad, hyaline, sparsely septate hyphae. These exhibit irregular right-angled branching and are predominantly observed at the periphery of the lesion.1
Waldenström macroglobulinemia (WM) is a lymphoplasmacytic lymphoma characterized by the presence of a monoclonal IgM protein. Recommended first-line therapies include chemoimmunotherapy or covalent Bruton tyrosine kinase (BTK) inhibitors. Although ibrutinib and zanubrutinib ‒ both covalent BTK inhibitors ‒ demonstrate high efficacy and favorable safety profiles, the prevalence of neutropenia and infections decreases over time with continued treatment.9 Nevertheless, attention should be paid to the infectious risks associated with these agents. To improve the cure rate of cutaneous mucormycosis, a multidisciplinary approach is essential. The preferred antifungal agent is the deoxycholate formulation of amphotericin B. In vitro susceptibility testing reveals variable activity of azole derivatives against species of the order Mucorales. Among them, posaconazole demonstrates the strongest activity, followed by isavuconazole; itraconazole displays limited activity, while voriconazole is inactive.1 Itraconazole may serve as a feasible alternative therapy for localized primary cutaneous mucormycosis occurring in sites other than the head and face.10
ORCID IDYuhua Weng: 0009-0001-5489-4922
Zehu Liu: 0000-0002-1472-411X
Ethical approval statementWritten and informed consent was obtained from this patient. The study was approved by the Medical Ethics Committee of Hangzhou Third People's Hospital (nº2025KA240).
Research data availabilityDoes not apply.
Financial supportThe study was supported by The Construction Fund of Key Medical Disciplines of Hangzhou (nº2025HZGF07).
Authors' contributionsYuhua Weng: Designed the study; performed the research and contributed to analysis and interpretation of data; wrote the initial draft of the manuscript; read and approved the final version of the manuscript.
Zehu Liu: Designed the study; performed the research and contributed to analysis and interpretation of data; assisted in the preparation of the manuscript; read and approved the final version of the manuscript.
Xiujiao Xia: Designed the study; performed the research and contributed to analysis and interpretation of data; wrote the initial draft of the manuscript; read and approved the final version of the manuscript.
Conflicts of interestNone declared.
The authors wish to thank the patient for his willingness to share his experience by providing informed consent for this case report.
Study conducted at the Department of Dermatology, Hangzhou Third People’s Hospital, Zhejiang Chinese Medical University, Hangzhou, China.


